When a child wakes up with a sore throat and fever, many parents wonder if it might be strep throat. Rapid strep tests help doctors quickly check for group A streptococcus, the bacteria that cause most cases of classic strep throat. Knowing what this test is, how it works, and what the results mean can make the experience less stressful for you and your child.
What Is Strep Throat and Why Does It Matter?
Strep throat is an infection of the throat and tonsils caused most often by group A Streptococcus (GAS) bacteria. These germs spread through respiratory droplets when an infected person coughs, sneezes, or shares food and drinks.
In children, strep throat is important to identify because:
- It can cause significant throat pain and fever.
- It is contagious and can spread quickly in schools and day care.
- Antibiotics can shorten symptoms slightly and reduce spread to others.
- Treating confirmed group A strep infections helps prevent rare but serious complications such as rheumatic fever and some kidney problems.
Because many viruses can cause similar symptoms, doctors rely on tests rather than symptoms alone to decide whether antibiotics are needed.
Why Doctors Use a Rapid Strep Test
A rapid strep test is a quick test done in the clinic to look for antigens (pieces of the bacteria) from group A Streptococcus in a throat sample. It typically gives results in minutes.
Clinicians often choose a rapid test when a child has:
- Moderate to severe sore throat without typical cold symptoms.
- Fever, swollen tonsils, or white patches on the tonsils.
- Tender or swollen glands in the neck.
- Known exposure to someone recently diagnosed with strep throat.
These tests are used because they are:
- Fast – results usually in 5–10 minutes.
- Simple – done at the point of care without a full laboratory.
- Specific – a positive result strongly suggests true group A strep infection.
Types of Tests Used for Suspected Strep Throat
When a child is tested for strep, several different methods may be used. Each has strengths and limits.
| Test Type | What It Detects | Typical Timing | Accuracy Highlights | Common Use |
|---|---|---|---|---|
| Rapid Antigen Detection Test (RADT) | Strep A antigens from a throat swab | Results in about 5–10 minutes | Average sensitivity about 85–86%; specificity about 95% in children. | First-line office test for many kids with suspected strep throat |
| Rapid Molecular / PCR Strep Test | Genetic material (DNA/RNA) of group A strep | Often 5–15 minutes depending on device | High sensitivity and specificity, often over 94% and 98% respectively in clinical studies. | Used in some clinics and urgent care centers as an alternative to antigen tests |
| Throat Culture | Live group A strep bacteria grown from throat swab | Results usually in 24–48 hours | Considered the reference standard for diagnosis; more sensitive than many rapid antigen tests. | Backup test when rapid tests are negative but suspicion remains high |
How the Rapid Strep Test Is Done
The procedure is quick, but preparing your child can help it go smoothly. The test usually includes these steps:
- Medical history and exam: The clinician asks about symptoms (fever, cough, runny nose, exposure to illness) and examines the throat, tonsils, and neck glands.
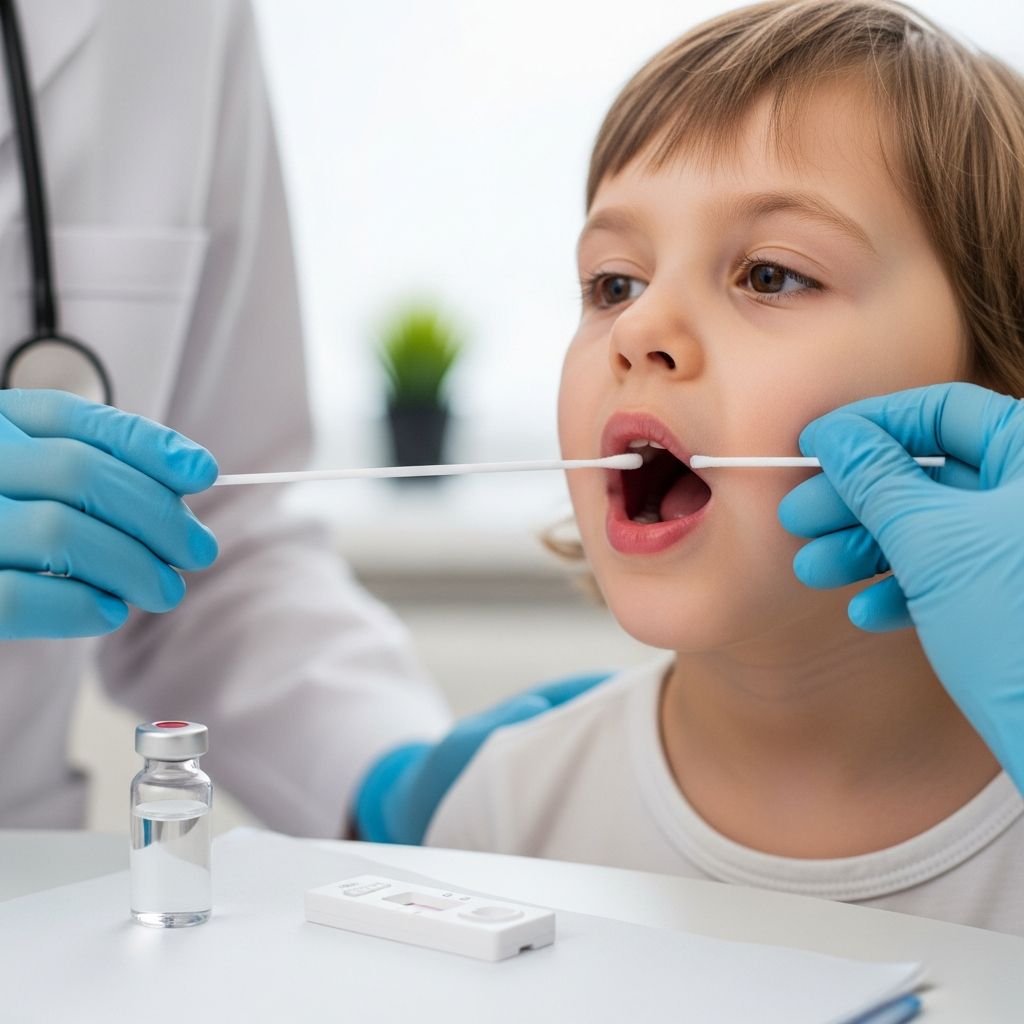
- Throat swab: A soft cotton or polyester swab is gently rubbed over the tonsils and the back of the throat, avoiding the tongue and cheeks.
- Sample processing: The swab is placed into a testing solution or device that checks for group A strep.
- Reading the result: After several minutes, the team reads whether the test is positive or negative.
Children may find the swab uncomfortable and may gag, but it is safe and brief. Taking a deep breath, looking up, and staying still usually help the test go faster.
Helping Your Child Get Ready
Parents can ease anxiety by describing the test in simple, reassuring terms before arriving at the clinic. Consider these tips:
- Explain that the doctor will “tickle” the back of the throat with a soft Q-tip-like stick.
- Practice saying “aaah” and opening wide in a mirror at home.
- Let older kids know the test helps the doctor decide whether they truly need medicine.
- Bring a comfort item such as a small toy or stuffed animal for younger children.
In most cases there is no need to change your child’s eating or drinking beforehand. If your child recently used throat lozenges, sprays, or strong mouthwash, tell the clinician so they can decide whether it may affect sample collection.
Understanding Rapid Strep Test Accuracy
No test is perfect. Parents often ask how reliable a rapid strep test is, and whether they can trust the result. Researchers have studied thousands of children to better understand this.
Accuracy of Rapid Antigen Tests
Large reviews of rapid antigen detection tests (RADTs) in children show that, on average:
- Sensitivity (how often the test finds strep when it is really there) is about 85–86%.
- Specificity (how often the test is negative when there is no strep) is about 95%.
In practical terms, if 100 children truly have strep throat, an average rapid antigen test may correctly detect around 86 of them and miss about 14. If 100 children do not have strep, about 95 will test negative and 5 may have a false-positive result.
Accuracy can vary between clinics and depends on correct swabbing and test handling. Studies have shown that proper training of staff improves test sensitivity.
Accuracy of Rapid Molecular (PCR) Tests
Newer rapid nucleic acid (molecular) tests detect the bacteria’s genetic material and are generally more sensitive than older antigen tests. For example:
- Meta-analyses of rapid nucleic acid tests for group A strep report average sensitivity around 97.5% and specificity around 95%.
- Real-world urgent care studies of point-of-care strep PCR have found specificities close to 99% with very few false negatives compared with throat culture.
These tests can reduce the need for backup cultures, but their use depends on clinic resources and local practice patterns.
What a Positive or Negative Result Means
Positive Rapid Strep Result
A positive rapid strep test usually means that group A Streptococcus is present in the throat sample. Because specificity is high, a positive result is considered very reliable.
When the test is positive, clinicians typically:
- Diagnose the child with strep throat (group A strep pharyngitis).
- Prescribe an appropriate antibiotic, most often a penicillin-family drug if the child is not allergic.
- Explain how long the child will be contagious (often up to 24 hours after starting antibiotics) and give school/daycare return guidance.
In some situations, kids may carry group A strep bacteria in their throat without being truly sick from it. The doctor will use your child’s symptoms and exam findings along with the test result to decide whether treatment is needed.
Negative Rapid Strep Result
A negative rapid strep test suggests that group A strep was not found in the sample. However, because sensitivity is not 100%, some true infections may be missed.
Next steps depend on the type of rapid test and your child’s risk level:
- After a negative antigen test in a child with strong signs of strep throat, many clinicians send a backup throat culture, which is more sensitive.
- After a negative PCR test, which is more sensitive, a backup culture is less commonly required, but individual practices vary.
- If the doctor believes the illness is more likely viral (for example, cough, runny nose, hoarseness, mouth sores), they may not test further and will usually not prescribe antibiotics.
If a culture is sent, you may be asked to wait 1–2 days for final results. During that time, your child’s symptoms are usually treated with rest, fluids, and comfort measures such as acetaminophen or ibuprofen if needed.
Possible Risks and Discomforts
Rapid strep testing is very safe. The main issues are mild and short-lived:
- Brief gagging when the swab touches the back of the throat.
- A slight tickling or scratching sensation.
- Very rarely, minor throat irritation after the swab.
There is no exposure to radiation, needles, or anesthesia. Serious complications from the test itself are extremely uncommon.
How Results Affect Treatment Decisions
Tests for strep throat help guide responsible antibiotic use. Giving antibiotics only when they are truly needed has several benefits:
- Reduces side effects such as diarrhea, rashes, and allergic reactions.
- Helps slow the development of antibiotic-resistant bacteria.
- Avoids unnecessary medicine costs and doctor visits.
Because typical cold viruses do not respond to antibiotics, a negative strep test often reassures families that supportive care at home is the right approach. A positive test, on the other hand, supports starting antibiotics to shorten contagiousness and prevent rare complications.
When to Call the Doctor After Testing
After a rapid strep test, contact your child’s healthcare provider promptly if:
- Fever lasts more than 48–72 hours, or returns after improving.
- Breathing or swallowing becomes difficult.
- Your child develops a new rash, joint pain, or dark/bloody urine in the days or weeks after illness.
- Symptoms worsen despite antibiotics, or your child seems unusually tired or ill.
These changes may signal complications or a different diagnosis and should be evaluated urgently.
Key Questions to Ask Your Child’s Provider
To understand your child’s care plan, you might ask:
- Which type of strep test are you using (antigen, PCR, or both)?
- If the rapid test is negative, will you send a throat culture?
- Does my child need antibiotics today, or should we wait for additional results?
- When can my child return to school or daycare?
- What signs should make us come back or go to urgent care?
Frequently Asked Questions (FAQs)
How long does a rapid strep test take?
Most rapid strep antigen or molecular tests give a result in about 5–10 minutes, though some devices can take slightly longer. You and your child can usually wait in the exam room for the answer.
Is the throat swab painful?
The swab is not painful, but it can be uncomfortable. Children often describe it as a tickle or a strong urge to gag. The entire swab usually takes just a few seconds.
Can my child eat or drink before the test?
In routine situations, eating and drinking are allowed before the test. If your child has just had a throat spray, lozenge, or very strong mouthwash, tell the clinician so they can decide whether to wait briefly before swabbing.
If the rapid test is negative, does that rule out strep throat?
Not always. Rapid antigen tests can miss some true infections, which is why many clinicians send a backup throat culture in children with a strong clinical picture of strep throat.
Why not skip testing and just give antibiotics if the throat looks bad?
Symptoms and physical exam alone cannot reliably distinguish viral sore throats from true group A strep infections. Testing helps avoid unnecessary antibiotics for viral illnesses while still treating confirmed strep throat appropriately.
Can my child get strep throat again after treatment?
Yes. Children can get strep throat more than once, especially during the school year. Each new episode should be evaluated by a healthcare professional, who may repeat testing based on symptoms and exam findings.
References
- Rapid antigen detection test for group A streptococcus in children with pharyngitis — Cohen JF et al., Cochrane Database of Systematic Reviews. 2016-07-14. https://pmc.ncbi.nlm.nih.gov/articles/PMC6457926/
- Diagnostic accuracy of a rapid nucleic acid test for group A streptococcus in children using saliva — Llor C et al., BMC Primary Care. 2023-05-18. https://pmc.ncbi.nlm.nih.gov/articles/PMC10347703/
- Real-World Validation of Rapid PCR Strep Testing in Urgent Care — Athey T et al., Journal of Urgent Care Medicine. 2021-02-01. https://www.jucm.com/real-world-validation-of-rapid-pcr-strep-testing-in-urgent-care/
- Accuracy of Rapid Strep Testing vs. Throat Culture — American Academy of Family Physicians. 2002-12-15. https://www.aafp.org/pubs/afp/issues/2002/1215/p2297.html
- Performance of Rapid Streptococcal Antigen Testing Varies by Personnel and Use of On-site Backup Culture — Roggenkamp A et al., Journal of Clinical Microbiology. 2007-02-01. https://journals.asm.org/doi/10.1128/jcm.01399-06