

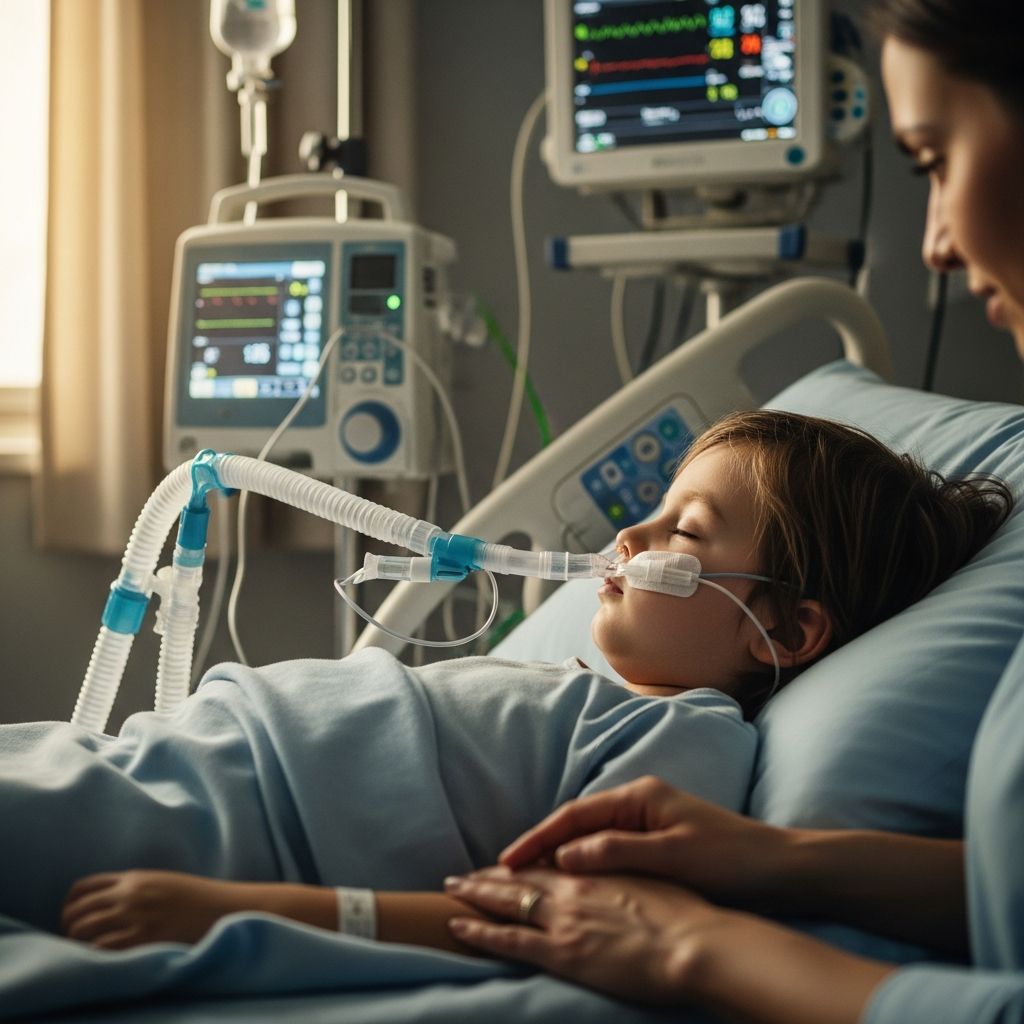
Respiratory challenges in children can arise from various conditions like infections, surgeries, or chronic illnesses, often requiring mechanical breathing assistance through ventilators. These devices take over or support the lungs’ work, ensuring oxygen delivery and carbon dioxide removal. Understanding ventilators empowers parents to actively participate in their child’s care journey, whether in a hospital intensive care unit or at home.
Why Children Might Need Breathing Machines
Youngsters face breathing difficulties due to acute issues such as pneumonia, severe asthma attacks, or trauma, or chronic ones like cystic fibrosis and neuromuscular disorders. Newborns, especially premature ones, may rely on ventilators for respiratory distress syndrome. Post-surgery, particularly after heart or chest procedures, these machines prevent fatigue while lungs heal. Early intervention with ventilators stabilizes oxygen levels, averting organ damage.
- Acute respiratory failure: From viruses like RSV or bacterial infections overwhelming small airways.
- Chronic lung diseases: Conditions impairing natural breathing over time.
- Surgical recovery: Temporary support during anesthesia recovery.
- Neuromuscular issues: Weak muscles failing to expand lungs adequately.
Types of Ventilators Used in Pediatric Settings
Healthcare providers select ventilators based on a child’s age, size, and condition severity. Infant-specific models differ from those for older kids, featuring smaller tubing and gentler pressure settings to match developing lungs.
| Type | Description | Best For |
|---|---|---|
| Non-Invasive (NIV) | Delivers air via mask or nasal prongs, avoiding tube insertion. | Mild cases, sleep apnea, weaning phase. |
| Invasive (via tracheostomy or ET tube) | Direct airway connection for full control. | Severe failure, unconscious patients. |
| High-Frequency Oscillatory (HFO) | Rapid, tiny breaths to minimize lung injury. | Premature infants, ARDS. |
| Portable/Home Units | Battery-powered, lightweight for mobility. | Long-term home care. |
Customization ensures minimal barotrauma—lung damage from excessive pressure—crucial for delicate pediatric airways.
How These Devices Work to Aid Breathing
Ventilators connect to the child’s airway through an endotracheal tube, tracheostomy, or mask. They monitor vital signs like oxygen saturation and adjust airflow automatically. Modes vary: volume-controlled delivers fixed air amounts; pressure-controlled limits force to protect tissues. Alarms alert for tube blockages, low oxygen, or disconnections, allowing swift responses.
Key components include:
- Air/oxygen blender: Mixes precise gas ratios.
- Humidifier: Prevents airway drying.
- Sensors: Track pressure, volume, and flow.
- Display screens: Show real-time data for clinicians.
The Setup and Monitoring Process in Hospitals
Intubation or tracheostomy placement occurs under sedation. Nurses secure tubes with ties or cuffs, then calibrate the machine to tidal volume (air per breath, often 6-8 ml/kg for kids) and respiratory rate (matching age norms: 30-60/min for infants). Continuous monitoring via pulse oximetry, capnography, and blood gases guides adjustments. Parents observe from beside, learning readouts.
Weaning begins when the child breathes independently more, gradually reducing support over days or weeks.
Life at Home with a Pediatric Ventilator
Many children transition home with ventilators, especially those with stable chronic needs. Training equips families: daily cleaning prevents infections, battery checks ensure portability, and emergency protocols prepare for power outages. Home health nurses visit, but parents manage routine care, fostering normalcy like school attendance.
- Cleaning circuits daily with sterile water.
- Monitoring skin around tube sites for irritation.
- Stocking backup batteries and supplies.
Caring for Your Child’s Comfort and Emotional Well-Being
Tubes can irritate throats, causing discomfort; suctioning removes secretions gently. Position changes and humidified air soothe. Emotionally, kids may feel scared—reassure with stories, toys, and presence. Siblings benefit from explanations to reduce anxiety. Play therapy adapts to bedbound states.
Risks, Complications, and Prevention Strategies
Potential issues include ventilator-associated pneumonia (VAP) from bacteria, atelectasis (lung collapse), or barotrauma. Prevention: elevated bed heads, oral care, minimal sedation. Regular X-rays and cultures detect problems early. Long-term, monitor growth and neurodevelopment.
| Complication | Signs | Prevention |
|---|---|---|
| VAP | Fever, increased secretions | Hand hygiene, circuit changes |
| Tube dislodgement | Alarms, breathing distress | Secure ties, frequent checks |
| Skin breakdown | Redness at site | Padding, repositioning |
Working with Your Healthcare Team Effectively
Respiratory therapists, intensivists, and nurses form the core team. Ask about settings, weaning plans, and home transition. Attend rounds, voice concerns—your insights aid decisions. Prepare questions:
- How long until weaning?
- What infection signs to watch?
- Home equipment needs?
Future Advances in Pediatric Respiratory Support
Technology evolves: AI-monitored ventilators predict desaturations; neurally adjusted ventilatory assist (NAVA) syncs with diaphragm signals for natural breathing. Non-invasive innovations like high-flow nasal cannula reduce intubation needs. These promise shorter support durations and better outcomes.
Frequently Asked Questions (FAQs)
Can my child talk with a ventilator?
With a tracheostomy speaking valve or around an uncuffed tube, yes, during ventilator pauses. Passy-Muir valves aid voicing.
How do I know if weaning is succeeding?
Improved blood gases, spontaneous breathing trials without distress, and stable vitals indicate progress.
Is home ventilation safe for toddlers?
Yes, with thorough training, equipment, and follow-ups; thousands thrive at home annually.
What if the power goes out?
Battery backups last 8+ hours; manual resuscitation bags serve as bridges.
Will my child need this forever?
Many wean fully; chronic cases adapt long-term with growth-adjusted support.
References
- Pediatric Ventilator Management — American Thoracic Society. 2024-06-15. https://www.thoracic.org/statements/pediatric-ventilation.pdf
- Mechanical Ventilation in Children — NIH National Heart, Lung, and Blood Institute. 2023-11-20. https://www.nhlbi.nih.gov/health/ventilation-children
- Guidelines for Pediatric Acute Respiratory Distress Syndrome — Pediatric Acute Lung Injury and Sepsis Investigators. 2024-02-10. https://www.palsnetwork.com/pardsparadise
- Home Ventilation for Children — Centers for Disease Control and Prevention. 2025-01-05. https://www.cdc.gov/respiratory/home-ventilation.html
- Advances in Pediatric Mechanical Ventilation — World Health Organization. 2024-09-12. https://www.who.int/publications/ped-vent-advances
- Family-Centered Care in PICU — Society of Critical Care Medicine. 2023-12-18. https://www.sccm.org/resources/family-care



