

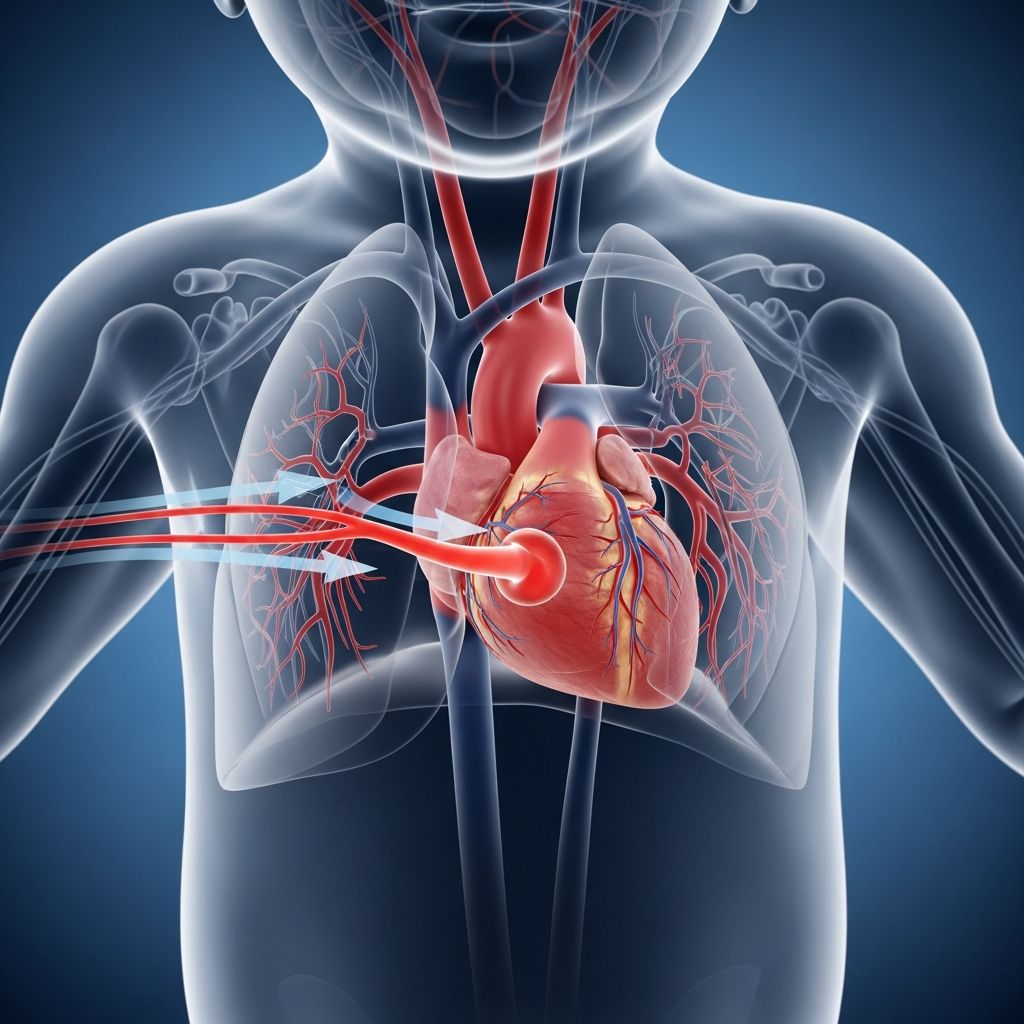
Patent ductus arteriosus (PDA) represents one of the most frequently encountered congenital heart anomalies, particularly affecting newborns and preterm infants. This condition arises when a natural fetal blood vessel fails to seal shut after birth, leading to abnormal circulation that can overburden the heart and lungs.
The Role of the Ductus Arteriosus in Fetal Development
During pregnancy, the fetus relies on the mother’s placenta for oxygen and nutrient delivery, bypassing the underdeveloped lungs. A critical structure known as the ductus arteriosus connects the pulmonary artery to the aorta, shunting oxygen-rich blood away from the lungs directly into the systemic circulation. This temporary vessel ensures efficient blood flow in the womb.
At birth, with the onset of breathing, oxygen levels rise, and prostaglandin levels drop, triggering the ductus to constrict and eventually close permanently within hours to days in full-term babies. In cases of PDA, this closure does not occur, resulting in a persistent opening that allows oxygenated blood from the aorta to recirculate back into the pulmonary artery.
Who Is at Risk for Developing PDA?
PDA occurs in approximately 5-10% of all congenital heart defects among term infants, with a significantly higher prevalence in premature babies due to the inverse relationship with gestational age and birth weight. Female infants are affected twice as often as males.
- Prematurity: The leading risk factor, as immature physiology disrupts normal closure mechanisms like oxygen sensitivity and prostaglandin regulation.
- Genetic factors: Certain chromosomal conditions, such as Down syndrome, increase susceptibility.
- Maternal health: Exposure to rubella during pregnancy or high-altitude living may elevate risks.
- Family history: Siblings with congenital heart issues raise the likelihood.
While many cases arise sporadically, understanding these risks helps in early screening for at-risk newborns.
Recognizing the Signs and Symptoms of PDA
The presentation of PDA varies widely based on the size of the persistent vessel and the infant’s age and maturity. Small PDAs may remain asymptomatic, discovered incidentally, while larger ones manifest early with clear distress signals.
| Symptom | Description | Common in |
|---|---|---|
| Heart murmur | Continuous ‘machinery-like’ sound heard via stethoscope | All symptomatic cases |
| Rapid or difficult breathing | Tachypnea or grunting due to lung fluid overload | Preterm infants |
| Poor feeding and weight gain | Fatigue during feeds from heart strain | Moderate to large PDAs |
| Bounding pulses and tachycardia | Strong peripheral pulses from high-output state | Larger defects |
| Sweating and irritability | Signs of congestive heart failure | Severe cases |
In preterm infants, symptoms often appear within the first week, escalating to heart failure if untreated. Older children with untreated small PDAs might show no issues until later complications arise.
How Doctors Diagnose PDA
Suspicion typically begins with a routine exam detecting a murmur, prompting referral to a pediatric cardiologist. Diagnostic confirmation relies on non-invasive imaging and tests.
- Echocardiogram (echo): Gold standard, visualizing the open ductus, blood flow direction, and heart strain via ultrasound.
- Chest X-ray: Reveals enlarged heart or excess lung fluid.
- Electrocardiogram (ECG): Checks for chamber enlargement or arrhythmias.
- Cardiac catheterization: Rarely needed for diagnosis but useful pre-procedure.
Early diagnosis is crucial, especially in NICU preterm babies where PDA contributes to respiratory distress syndrome.
Treatment Options: From Medications to Surgery
Management prioritizes closure to avert complications like pulmonary hypertension, heart failure, or endocarditis. Approach depends on PDA size, symptoms, and infant stability.
Pharmacological Closure
Indomethacin or ibuprofen, non-steroidal anti-inflammatory drugs, inhibit prostaglandins to promote ductal constriction. Administered intravenously, they succeed in 70-80% of preterm cases, ideally within the first two weeks.
Catheter-Based Intervention
A minimally invasive preferred method for most infants and children. A coil or device is deployed via a groin catheter to occlude the ductus under X-ray guidance. Success rates exceed 95% with low risks.
Surgical Ligation
Reserved for large PDAs, failed medications, or very premature infants. Performed via thoracotomy, the ductus is tied off. Highly effective but involves general anesthesia and brief recovery.
Observation suits tiny, asymptomatic PDAs that may close spontaneously by age 1.
Potential Complications of Untreated PDA
Prolonged patency floods lungs with blood, causing:
- Pulmonary congestion and hypertension.
- Left heart enlargement and failure.
- Increased endocarditis risk.
- Rarely, Eisenmenger syndrome in adulthood from reversed shunt.
Prompt intervention mitigates these, restoring normal circulation.
Life After PDA Closure: Prognosis and Follow-Up
Post-treatment, most children thrive with normal activity levels and development. Catheter or surgical closure yields excellent outcomes, with <1% complication rates.
Regular cardiologist check-ups monitor growth and heart function. Antibiotic prophylaxis may be advised pre-dental procedures initially to prevent endocarditis.
Premature infants face higher risks of associated issues like bronchopulmonary dysplasia, but PDA closure improves respiratory support weaning.
Prevention Strategies and Rubella Vaccination
While most PDAs are unpreventable, maternal rubella vaccination reduces incidence linked to congenital rubella syndrome. Prenatal care and preterm birth prevention indirectly help.
Frequently Asked Questions About PDA
Can PDA close on its own without treatment?
Yes, small PDAs in term infants often seal spontaneously within the first year. Monitoring via echoes guides watchful waiting.
Is PDA more common in boys or girls?
It affects girls twice as frequently as boys.
What causes a baby to have PDA?
Primarily prematurity disrupts closure signals; genetic or environmental factors contribute in term babies.
How soon after birth is PDA treated?
In symptomatic preemies, within days to weeks; elective closure later for others.
Does PDA affect long-term heart health?
After successful closure, prognosis is excellent with no lasting effects in most cases.
References
- Patent ductus arteriosus: an overview — PubMed/NCBI. 2012-10-16. https://pubmed.ncbi.nlm.nih.gov/23055849/
- Patent Ductus Arteriosus — UCSF Department of Surgery. Accessed 2026. https://pedctsurgery.ucsf.edu/condition/patent-ductus-arteriosus
- Patent Ductus Arteriosus — Loyola Medicine. Accessed 2026. https://www.loyolamedicine.org/services/heart-and-vascular/heart-vascular-conditions/patent-ductus-arteriosus
- Patent Ductus Arteriosus (PDA) — Nemours KidsHealth. Accessed 2026. https://kidshealth.org/en/parents/patent-ductus-arteriosus.html
- Pediatric Patent Ductus Arteriosus (PDA) — Children’s National Hospital. Accessed 2026. https://www.childrensnational.org/get-care/health-library/patent-ductus-arteriosus-pda
- Patent Ductus Arteriosus (PDA) — American Heart Association. Accessed 2026. https://www.heart.org/en/health-topics/congenital-heart-defects/about-congenital-heart-defects/patent-ductus-arteriosus-pda
- Patent Ductus Arteriosus (PDA): Symptoms and Treatment — Cleveland Clinic. Accessed 2026. https://my.clevelandclinic.org/health/diseases/17325-patent-ductus-arteriosus-pda



