During the height of the COVID-19 pandemic, hospital births underwent unprecedented transformations as healthcare systems worldwide implemented strict protocols to curb virus transmission. New mothers navigated a landscape of isolation, virtual consultations, and masked medical teams, fundamentally altering one of life’s most intimate moments. This article delves into these shifts, drawing from global studies and firsthand accounts to illuminate the challenges and unexpected positives of delivering in a crisis.
Prenatal Care: From In-Person to Virtual Realms
Pregnancy monitoring shifted dramatically as clinics prioritized safety. Routine in-person ultrasounds and check-ups dwindled, replaced by telehealth sessions that offered convenience but lacked the tactile reassurance of physical exams. Women reported fewer visits—sometimes just two between mid-pregnancy scans and delivery—leaving many feeling disconnected from their care teams.
In regions like Andalusia, Spain, reorganization of services led to widespread anxiety over incomplete information and contagion fears. Participants in qualitative studies highlighted how these changes eroded trust, with virtual calls failing to replicate the empathy of face-to-face interactions. Yet, this pivot to digital care expanded access for some, allowing remote monitoring of fetal heart rates via home devices.
- Key adaptations: Video consultations every two weeks supplemented essential scans.
- Challenges: Solo attendance at mandatory appointments heightened emotional strain.
- Benefits: Reduced exposure risks while maintaining continuity.
These modifications underscored a broader tension: balancing maternal health with viral threats, often at the expense of personalized support.
Hospital Protocols: Safety Measures and Isolation
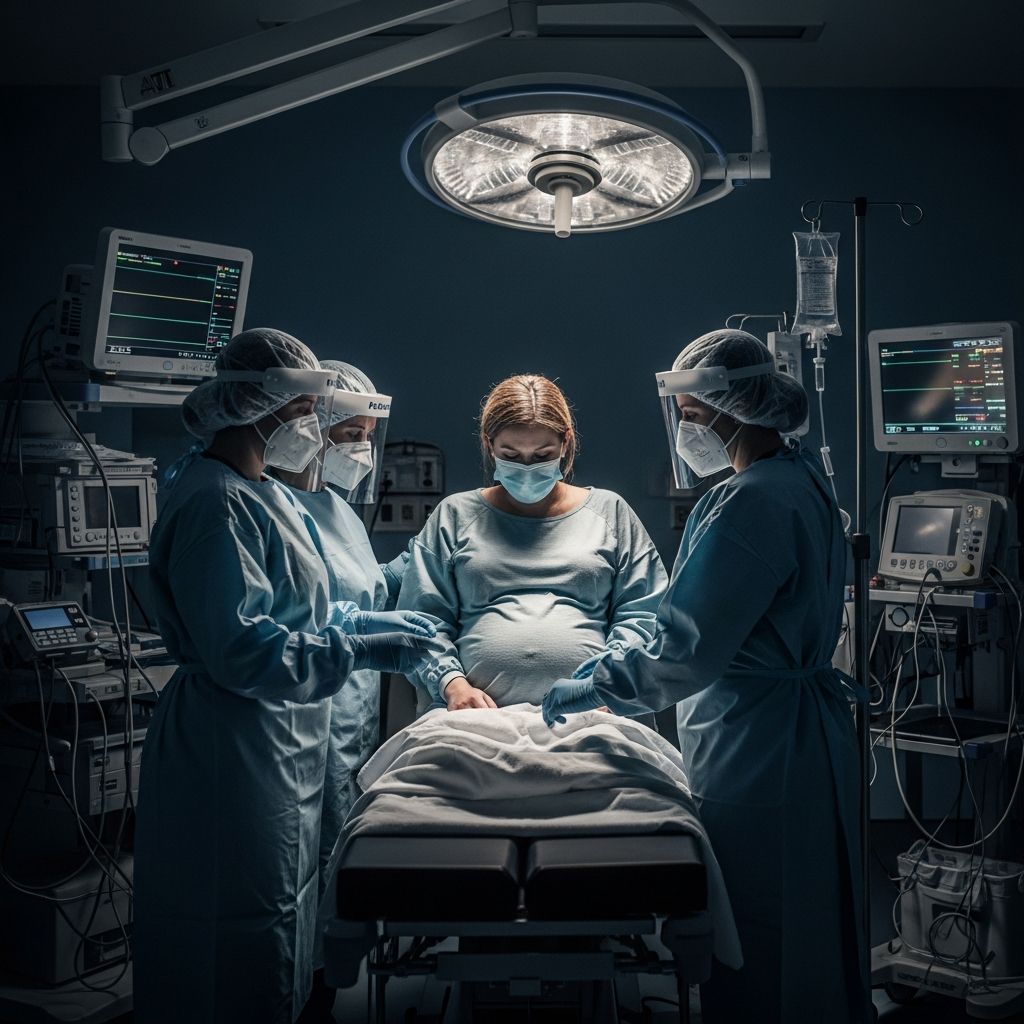
Upon arrival at labor and delivery wards, birthing individuals encountered a fortress of precautions. Full personal protective equipment (PPE) for staff, mandatory masking—even during pushes—and rigorous screening defined the new normal. While these steps fostered a sense of security, they also created barriers to emotional connection.
One of the most poignant restrictions was the exclusion of partners or doulas from delivery rooms. Early pandemic policies in the U.S. and Europe barred support persons, forcing many women to labor alone. This isolation amplified stress, as studies link social support to higher birth satisfaction. In the UK, women frequently altered plans, shifting from home births to hospitals only to face solitary experiences.
| Protocol Change | Impact on Mothers | Example Regions |
|---|---|---|
| Partner bans in labor | Increased anxiety, lower satisfaction | US, Spain, UK |
| Mandatory PPE/masks | Depersonalized care, muffled communication | Global hospitals |
| Screening at entry | Delays, added stress | Widespread |
| Limited mobility | Restricted movement in rooms | US facilities |
Despite these hurdles, many appreciated the heightened hygiene. Hospitals became sanctuaries of cleanliness, with fewer routine visitors reducing secondary infection risks.
Delivery Dynamics: Interventions and Unexpected Outcomes
The pandemic influenced birth modes and interventions. Data from U.S. hospitals showed unassisted vaginal births with epidurals as most common (46.7%), followed by planned cesareans (18.5%). However, fears of overwhelmed facilities prompted some to opt for out-of-hospital alternatives, though this trend was limited.
Restrictions like delayed skin-to-skin contact or neonate separation in positive cases disrupted bonding. Women expressed distress over masked babies and hazmat-suited obstetricians, elements that clashed with visions of serene deliveries. Uncertainty loomed large: Would protocols change mid-labor? Would family meet the newborn?
Conversely, quieter wards offered tranquility. Fewer visitors meant peaceful postpartum recoveries, allowing rest amid chaos. Birthing individuals in secure environments reported positive reflections on staff diligence.
Postpartum Realities: Bonding Amid Barriers
After birth, the isolation persisted. Visitor bans extended into recovery, severing traditional family introductions. Mothers juggled newborn care solo, compounded by mask mandates that obscured facial cues during feeding.
Studies emphasize social support’s role in satisfaction; prenatal partner and family backing correlated positively, even if absent at birth. In the U.S., women birthing between April and October 2020 described a mix of resilience and longing, with virtual hellos substituting physical embraces.
Positive notes emerged: Enhanced focus on mother-baby dyads without external distractions. Some facilities innovated with window visits or video calls, fostering connection creatively.
Global Variations: Lessons from Diverse Systems
Experiences varied by region. In Spain, hospital safety reassured despite prenatal gaps. U.S. policies fragmented, with states differing on partner allowances, leading to out-of-hospital upticks. The UK’s early strictures forced plan overhauls, underscoring policy inconsistency’s toll.
Emerging themes across studies: Fear drove caution, but robust measures built confidence. Qualitative insights from Andalusia highlight security during birth as a counterbalance to earlier woes.
Long-Term Emotional Echoes
Beyond immediate logistics, pandemic births left psychological imprints. Lower satisfaction scores linked to restrictions, with isolation exacerbating postpartum mood risks. Yet, many mothers reflected gratefully on healthy outcomes, viewing adaptations as necessary sacrifices.
Research calls for integrated policies to prevent future disruptions, advocating flexible support models. The era highlighted resilience, as women adapted to virtual networks and self-reliant coping.
Strategies for Future Crises: Building Resilience
Healthcare evolved with hybrid models: Telehealth permanence, PPE standardization, and contingency plans for support persons. Lessons include prioritizing mental health screenings and companion tech solutions like live-streaming births.
- Invest in doula telepresence.
- Maintain virtual prenatal options.
- Develop family-inclusive protocols.
These forward-thinking steps ensure birthing remains human-centered, even in turmoil.
Frequently Asked Questions
Were partners completely banned from all hospital births during COVID-19?
Many hospitals enforced strict no-visitor policies early on, excluding partners from labor and delivery, though some later allowed one support person with testing.
Did pandemic restrictions increase cesarean rates?
No significant universal spike, but fears led some to planned cesareans; vaginal births remained prevalent.
How did virtual prenatal care affect pregnancy outcomes?
It reduced in-person risks but raised concerns over missed issues; outcomes were generally comparable with proper follow-ups.
Was skin-to-skin contact possible under restrictions?
Often delayed or modified due to masking and separation protocols, impacting early bonding.
Did mothers feel safer in hospitals despite changes?
Yes, many cited rigorous cleaning and low visitor numbers as confidence boosters.
References
- My Experience Having a Baby During the COVID-19 Pandemic — American College of Obstetricians and Gynecologists (ACOG). 2020. https://www.acog.org/womens-health/experts-and-stories/the-latest/my-experience-having-a-baby-during-the-covid19-pandemic
- Childbirth experience during the COVID-19 pandemic — National Library of Medicine, PMC. 2023. https://pmc.ncbi.nlm.nih.gov/articles/PMC10038889/
- The impacts of the COVID-19 pandemic on birth satisfaction — National Library of Medicine, PMC. 2021. https://pmc.ncbi.nlm.nih.gov/articles/PMC8501233/
- Challenges and lessons learned birthing during the COVID-19 pandemic — Wiley Online Library. 2023-07-20. https://onlinelibrary.wiley.com/doi/full/10.1002/hsr2.1387
- Experiences of Women Who Gave Birth in US Hospitals During the COVID-19 Pandemic — University of Nebraska Experts. 2023. https://experts.nebraska.edu/en/publications/experiences-of-women-who-gave-birth-in-us-hospitals-during-the-co