

Decoding the Coombs Test for New Parents
When your newborn undergoes routine screening tests at the hospital, you may encounter medical terminology that feels overwhelming. One such test is the Coombs test, also known as the Direct Antiglobulin Test (DAT)—a blood test that checks for specific antibodies on your baby’s red blood cells. Understanding what this test measures and what a positive result means can help you navigate your baby’s early healthcare with greater confidence and clarity.
The Coombs test is a standard screening procedure performed on many newborns, particularly those showing signs of jaundice or those whose mothers have risk factors for blood group incompatibility. A positive Coombs test does not automatically indicate a serious problem, but it does signal that your healthcare team should monitor your baby more closely for potential complications. The presence of antibodies on red blood cells can increase the risk of hemolysis—the breakdown of red blood cells—which may lead to anemia or elevated bilirubin levels in your infant.
How the Coombs Test Works and When It’s Performed
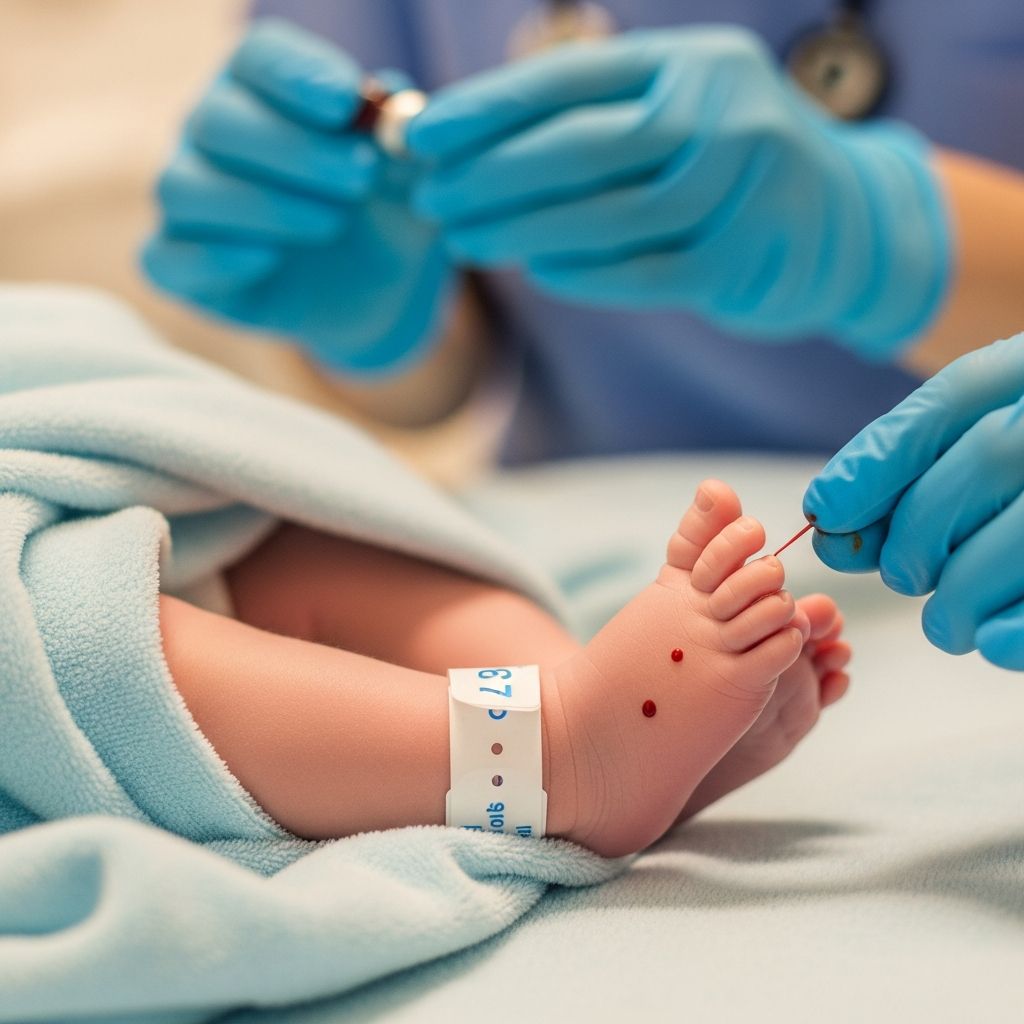
The Direct Coombs test is performed on a blood sample taken from your newborn, typically collected from the umbilical cord immediately after delivery or from a heel stick during the first few days of life. The test identifies antibodies that have attached to the surface of your baby’s red blood cells. These antibodies are usually produced by the mother’s immune system and cross the placenta during pregnancy or are transferred through the umbilical cord blood at delivery.
Healthcare providers use this test to diagnose hemolytic disease of the fetus and newborn (HDFN), a condition in which maternal antibodies attack fetal red blood cells. The test is particularly important for:
- Babies displaying visible jaundice in the first days of life
- Infants born to mothers with known blood group incompatibilities
- Newborns with a family history of hemolytic disease
- Babies showing signs of anemia or pallor at birth
An indirect Coombs test may also be performed on the mother’s blood during prenatal care to identify antibodies that could potentially affect the fetus. This screening allows healthcare providers to anticipate and prepare for potential complications before your baby is born.
Primary Causes of Positive Coombs Results in Newborns
A positive Coombs test in newborns typically stems from blood group incompatibilities between mother and infant. The most common causes include:
ABO Blood Group Incompatibility
ABO incompatibility occurs when the mother and baby have different ABO blood types. This is the most frequent cause of positive Coombs results, accounting for approximately 73.6 percent of positive cases in clinical studies. For example, if the mother has type O blood (which naturally contains anti-A and anti-B antibodies) and the baby has type A or B blood, the mother’s antibodies may attack the baby’s red blood cells. Fortunately, ABO incompatibility tends to cause milder disease compared to other blood group mismatches, though some infants still require treatment.
Rh Incompatibility
Rh incompatibility, also called Rh disease or erythroblastosis fetalis, occurs when an Rh-negative mother carries an Rh-positive baby. During pregnancy or delivery, fetal red blood cells containing the Rh antigen can enter the mother’s bloodstream, triggering her immune system to produce anti-D antibodies. These antibodies can cross back through the placenta and attack the baby’s red blood cells. While less common than ABO incompatibility due to preventive measures like Rh immune globulin injections, Rh disease can be more severe when it occurs.
Other Red Cell Alloantibodies
Occasionally, mothers develop antibodies against other blood group antigens beyond ABO and Rh systems. These non-ABO red cell alloantibodies account for approximately 20.4 percent of positive Coombs cases. These uncommon antibodies can develop through previous pregnancies, transfusions, or other exposures and may require specialized prenatal monitoring and treatment planning.
Preventive Injections and Test Results
Interestingly, Rh-negative pregnant women sometimes receive an injection called Rho(D) immune globulin to prevent sensitization. This protective measure can occasionally cause a positive Coombs test result in the newborn, though babies testing positive for this reason typically do not develop anemia or jaundice.
Recognizing Symptoms and Clinical Presentations
While a positive Coombs test indicates increased risk, not all babies with this result will develop noticeable symptoms. However, parents should be alert to signs that may suggest complications:
- Jaundice: Yellowing of the skin, sclera (whites of the eyes), and mucous membranes, typically appearing within the first 24 to 72 hours of life
- Excessive sleepiness: Your baby appears unusually drowsy, difficult to awaken, or unresponsive to feeding cues
- Pale appearance: Skin color appears lighter or washed out compared to healthy newborn coloring
- Feeding difficulties: Poor latch, weak sucking, or reluctance to feed despite hunger cues
- Lethargy: A floppy, low-muscle-tone appearance or minimal responsiveness to stimulation
- Bruising: Unexplained bruising on the body or face beyond typical birth trauma
It is crucial to understand that the presence of a positive Coombs test does not guarantee your baby will experience these symptoms. Research indicates that many infants with positive results remain asymptomatic and require only monitoring rather than intervention. Nevertheless, early recognition of these signs allows healthcare providers to initiate appropriate treatment promptly.
Treatment Approaches and Management Strategies
Treatment for babies with positive Coombs results depends on various factors, including the severity of hemolysis, bilirubin levels, the baby’s age and gestational maturity, and the underlying cause of the incompatibility.
Monitoring and Observation
Many Coombs-positive newborns require only close monitoring without intervention. Healthcare providers will perform regular blood tests to assess bilirubin levels and complete blood counts to check for anemia. Babies may be monitored in the hospital for several days or discharged home with scheduled follow-up appointments to ensure bilirubin levels remain within safe ranges. Frequent nursing or feeding—at least 8 to 12 times daily—supports natural bilirubin elimination through stool and urine.
Phototherapy
Phototherapy, commonly called blue light treatment, is the most frequent intervention for treating elevated bilirubin levels in Coombs-positive newborns. The blue and green wavelengths of light convert bilirubin into a water-soluble form that the baby’s body can eliminate more efficiently through urine and stool. Approximately 93.3 percent of newborns requiring treatment for jaundice need only phototherapy. During phototherapy, your baby lies under special lights, often with their eyes covered for protection. Treatment duration varies depending on bilirubin levels and the baby’s age.
Folic Acid Supplementation
When red blood cells are broken down prematurely, the body must work harder to create replacement cells. Folic acid supplementation supports this regenerative process and is often prescribed for Coombs-positive infants to help maintain adequate red blood cell production. This vitamin promotes healthy cell division and can help prevent anemia from developing.
Exchange Transfusion
In rare cases of severe hemolytic disease where bilirubin levels reach dangerous thresholds or anemia becomes profound, exchange transfusion may be necessary. This specialized procedure removes a portion of the baby’s blood and replaces it with donor blood, simultaneously reducing bilirubin levels and correcting anemia. Exchange transfusions are reserved for severe cases, occurring in fewer than 2 percent of Coombs-positive newborns, though they may be more common in cases involving Rh incompatibility or severe ABO mismatch.
Blood Transfusion
Standard blood transfusion may be needed if your baby develops significant anemia that compromises oxygen delivery to tissues or causes signs of heart strain. This is distinctly different from exchange transfusion and is considered when hemoglobin levels fall below critical thresholds.
Long-Term Outlook and Prognosis
The long-term prognosis for Coombs-positive newborns is generally excellent, particularly with appropriate monitoring and timely intervention. Most infants recover completely without lasting effects. The key concern—particularly in untreated severe cases—is kernicterus, a form of brain damage caused by extremely elevated bilirubin levels crossing into brain tissue. However, modern screening and treatment have made kernicterus rare in developed healthcare settings.
The severity of disease depends on multiple factors, including the type of blood group incompatibility, the strength of maternal antibodies, the baby’s gestational age at birth, and the promptness of intervention. Babies born at term with mild incompatibility typically have the best outcomes, while premature infants or those with severe antibody responses may require more intensive management.
Preparing for Your Baby’s Discharge and Home Care
Before leaving the hospital, parents of Coombs-positive babies should receive clear instructions about monitoring at home. Healthcare providers will schedule follow-up appointments, typically within 24 to 48 hours of discharge, to reassess bilirubin levels and overall health. Parents should know which symptoms warrant immediate medical attention and how to contact their healthcare team if concerns arise.
Ensuring adequate feeding is critical, as breast milk or formula helps move bilirubin through the digestive system and out of the body. Parents should track feeding frequency, wet diapers (at least 6 per day by day 5), and stool output (at least 3 per day after day 3). Keeping your baby in natural indirect sunlight may provide some benefit, though it should never replace prescribed phototherapy.
Important Warning Signs Requiring Immediate Care
While most Coombs-positive babies do well, certain symptoms require urgent medical evaluation:
- Increasing jaundice, particularly spreading to the chest, abdomen, or limbs
- High fever or signs of infection
- Poor feeding or refusal to feed
- Excessive sleepiness that prevents normal feeding or responses
- Unusual high-pitched crying or seizure-like movements
- Limp muscle tone or inability to support their head
These signs could indicate progression to kernicterus or other serious complications and demand immediate professional evaluation.
Common Questions About Coombs-Positive Results
Q: Does a positive Coombs test mean my baby will definitely become jaundiced?
A: No. While Coombs-positive babies have a higher risk for jaundice compared to negative babies, many do not develop jaundice requiring treatment. The presence of antibodies increases risk but does not guarantee disease development. Individual factors like blood type incompatibility severity, gestational age, and feeding success all influence outcomes.
Q: Will my baby need to stay in the hospital longer because of a positive Coombs test?
A: Extended hospitalization depends on your baby’s specific situation. Some Coombs-positive newborns are discharged within normal timeframes with close outpatient monitoring, while others may require additional hospital days for phototherapy or observation. Your healthcare team will determine the appropriate timeline based on bilirubin levels and clinical stability.
Q: Can I breastfeed if my baby is Coombs positive?
A: Yes, breastfeeding is encouraged and beneficial for Coombs-positive babies. Frequent nursing (8 to 12 times daily) promotes natural bilirubin elimination and helps prevent complications. Your healthcare team may also monitor weight gain to ensure adequate milk intake.
Q: Will this condition affect my baby’s health later in childhood or adulthood?
A: For most infants, positive Coombs results in the newborn period have no lasting impact on long-term health. Once the maternal antibodies naturally clear from the baby’s system over weeks to months, hemolysis stops and the baby’s red blood cells function normally. The exception would be if untreated severe cases led to kernicterus, which can cause lifelong neurological problems, but modern care has made this outcome extremely rare.
Q: If I’m Rh negative, does this mean future pregnancies will have problems?
A: If you received Rho(D) immune globulin during pregnancy and after delivery, you were protected from developing sensitization. This means future Rh-positive pregnancies should not be affected by Rh disease. However, if you were already sensitized before the first pregnancy, future pregnancies with Rh-positive babies carry increased risk and require specialized prenatal monitoring.
Q: What tests will my baby need if the Coombs test is positive?
A: Your healthcare team will typically order a complete blood count to check hemoglobin levels for anemia, a serum bilirubin test to measure jaundice levels, and possibly a reticulocyte count to assess the bone marrow’s response to red blood cell loss. These tests help determine whether treatment is needed and guide management decisions.
Empowering Yourself With Knowledge
Receiving news that your newborn has a positive Coombs test can feel frightening, but understanding what this test means, the range of possible outcomes, and the effective treatments available can help you feel more confident and prepared. The vast majority of Coombs-positive babies do well with appropriate monitoring and, when needed, timely intervention. By maintaining close follow-up with your healthcare team, watching for warning signs, and following their recommendations for feeding and monitoring, you are taking important steps to support your baby’s health and development during this critical period.
Remember that a positive Coombs test is a laboratory finding that indicates increased vigilance is warranted—not a diagnosis of disease. Your baby’s healthcare team has the expertise and tools to manage this situation effectively, and most children born with this finding go on to enjoy perfectly healthy lives without lasting complications or restrictions.
References
- My baby is Coombs positive. What’s D.A.T.? — Saint Louis Children’s Hospital. 2024. https://www.stlouischildrens.org/health-resources/pulse/baby-coombs
- The Coombs’ Test — Stanford Medicine, Newborn Nursery. 2024. https://med.stanford.edu/newborns/professional-education/jaundice-and-phototherapy/the-coombs–test.html
- Positive Coomb’s test in newborns; causes and clinical significance — Jonsson H, et al. PubMed/NCBI. 2016. DOI: 10.1186/s12887-016-0675-y. https://pubmed.ncbi.nlm.nih.gov/27531851/
- Coombs Test: Purpose, Procedure & Results — Cleveland Clinic. 2024. https://my.clevelandclinic.org/health/diagnostics/22978-coombs-test
- Parent information leaflet: Direct Coombs Test — NHS East of England Neonatal PDC & SICNet. 2022. https://eoeneonatalpccsicnetwork.nhs.uk/wp-content/uploads/2022/09/Parent-information-leaflet-Direct-Coombs-Test.pdf
- Coombs test — UCSF Benioff Children’s Hospitals. 2024. https://www.ucsfbenioffchildrens.org/medical-tests/coombs-test



