

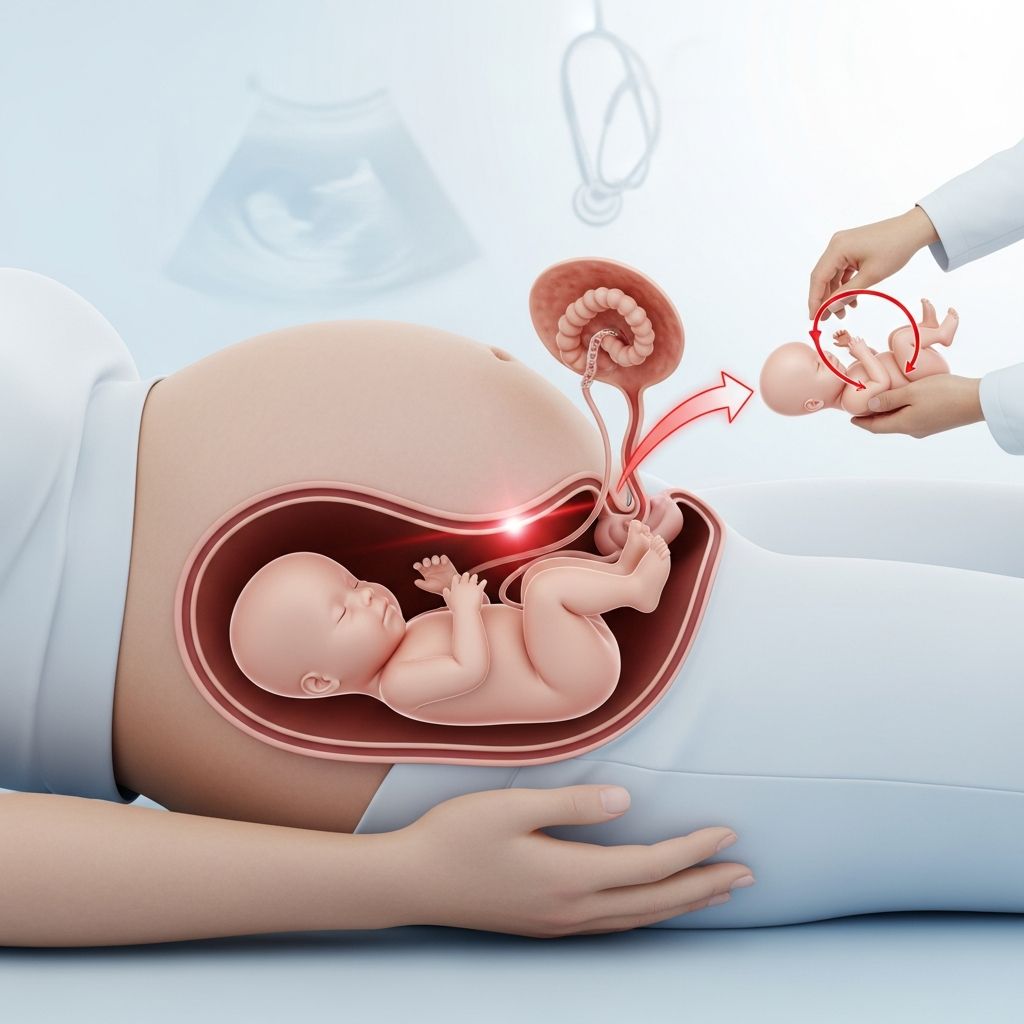
A transverse baby lies horizontally across the uterus, with the head on one side and bottom on the other, rather than in the ideal head-down position for birth. This uncommon presentation after 34 weeks raises concerns for delivery safety, often necessitating medical intervention to reposition the baby or plan a cesarean section.
Understanding Fetal Positions in Late Pregnancy
During early pregnancy, babies frequently shift positions due to ample space in the womb. By the third trimester, around 32-36 weeks, most settle into a vertical orientation, preferably cephalic (head-down), to align with the birth canal. Transverse lie, where the baby rests sideways, occurs in about 1 in 400-500 term deliveries, though it’s more frequent earlier in gestation.
The three primary fetal positions include:
- Cephalic (vertex): Head down, optimal for vaginal birth, seen in over 95% of full-term pregnancies.
- Breech: Bottom or feet down, manageable vaginally in some cases but riskier.
- Transverse: Sideways, preventing natural descent through the pelvis.
While transverse positioning is harmless before 32 weeks, persistence beyond this point prompts action to avoid complications.
Factors Leading to Sideways Fetal Positioning
Several anatomical and pregnancy-related elements can cause a baby to favor a transverse lie:
- Uterine abnormalities: A bicornuate (heart-shaped) uterus or septate uterus limits space, encouraging sideways settling.
- Placental location: A low-lying or anterior placenta occupies space needed for head engagement.
- Multiple gestation: Twins or triplets reduce room, with the second baby often transverse until the first delivers.
- Polyhydramnios or oligohydramnios: Excess or low amniotic fluid alters buoyancy and movement.
- Maternal history: Multiparous women (multiple prior pregnancies) have laxer uterine muscles, allowing more fetal mobility.
- Prematurity: Early deliveries increase transverse incidence due to incomplete settling.
These factors don’t always predict transverse lie but elevate risk, warranting ultrasound monitoring from 34 weeks.
Recognizing Signs of Transverse Lie
Mothers may notice distinct clues by palpating the abdomen:
- Hard round mass (head) on one side, softer buttocks on the other.
- Kicks or movements felt high across the belly or toward the mother’s back.
- A straight horizontal ridge across the abdomen when feeling the baby’s back.
- Shoulder or back pressing low near the pelvis in some variants.
Fundal height measurements may appear inconsistent, and Leopold’s maneuvers during checkups confirm position. Ultrasound provides definitive diagnosis, often routine after 36 weeks if breech or transverse is suspected.
Potential Dangers During Labor and Delivery
A transverse baby cannot engage in the pelvis, blocking vaginal birth. Key risks include:
| Risk | Description | Consequence |
|---|---|---|
| Umbilical cord prolapse | Cord slips ahead of baby if membranes rupture | Oxygen deprivation, emergency C-section |
| Obstructed labor | Baby’s shoulder impacts pelvis | Prolonged labor, uterine rupture risk |
| Birth trauma | Pressure on folded shoulder/neck | Injury to baby, postpartum hemorrhage |
| Maternal complications | Failed induction attempts | Infection, heavy bleeding |
If labor begins transversely, immediate cesarean is standard to mitigate these threats. Cord prolapse, in particular, demands delivery within minutes.
Non-Invasive Techniques to Reposition Baby
Before medical procedures, evidence-based exercises may encourage rotation:
- Forward-leaning inversion: Kneel on couch edge, lower torso to floor for 5-10 minutes daily to create pelvic space.
- Side-lying with peanut ball: Lie on side hugging a peanut-shaped ball to open pelvis.
- Moxibustion: Burn mugwort near acupuncture point BL67 to stimulate fetal movement (consult provider).
- Swimming or yoga: Buoyancy aids repositioning; poses like child’s pose promote cephalic turn.
- Chiropractic Webster technique: Balances pelvic ligaments to optimize uterine shape.
Success varies, highest before 37 weeks. Track with daily position checks and ultrasounds.
Medical Procedures for Turning Transverse Babies
External cephalic version (ECV) is the gold standard intervention, performed at 37-39 weeks. A specialist applies firm abdominal pressure to rotate the baby head-down externally, under ultrasound guidance and monitoring. Success rates hover at 50-60%, higher in multiparous women or with adequate fluid. Risks are low (1-2% complications like placental abruption), with tocolytics often used to relax the uterus.
If ECV fails or baby reverts, cesarean scheduling ensures safety. For multiples, vaginal delivery of the first may allow the second to turn naturally.
Planning Delivery Options
Most transverse cases end in planned C-section around 39 weeks to preempt rupture risks. VBAC candidates face added uterine rupture concerns. Discuss with providers:
- ECV timing and eligibility.
- Induction post-successful ECV.
- C-section preparation and recovery.
Early detection via routine scans optimizes outcomes.
Frequently Asked Questions
Can a transverse baby turn on its own after 36 weeks?
Possible but rare; most settle by 36 weeks. Monitor closely and consider interventions.
Is transverse lie dangerous before 34 weeks?
No, ample space allows movement. Concern arises later as space tightens.
How effective is ECV for transverse babies?
About 59% success, per studies, versus higher for breech.
Does transverse position affect pregnancy symptoms?
May cause more discomfort from kicks across belly but no major health impacts.
Can I prevent transverse lie?
Not always, but pelvic balancing exercises from mid-pregnancy help.
References
- How to Turn a Transverse Baby (and Avoid a C-Section) — The VBAC Link. 2023. https://www.thevbaclink.com/transverse-baby/
- What to Know About the Transverse Baby Position — The Bump. 2024. https://www.thebump.com/a/transverse-baby
- Can You Get Your Transverse Baby to Turn? — Healthline. 2023-10-15. https://www.healthline.com/health/pregnancy/transverse-baby
- Sideways/Transverse – Transverse Baby Position — Spinning Babies. 2024. https://www.spinningbabies.com/pregnancy-birth/baby-position/sideways-transverse/



