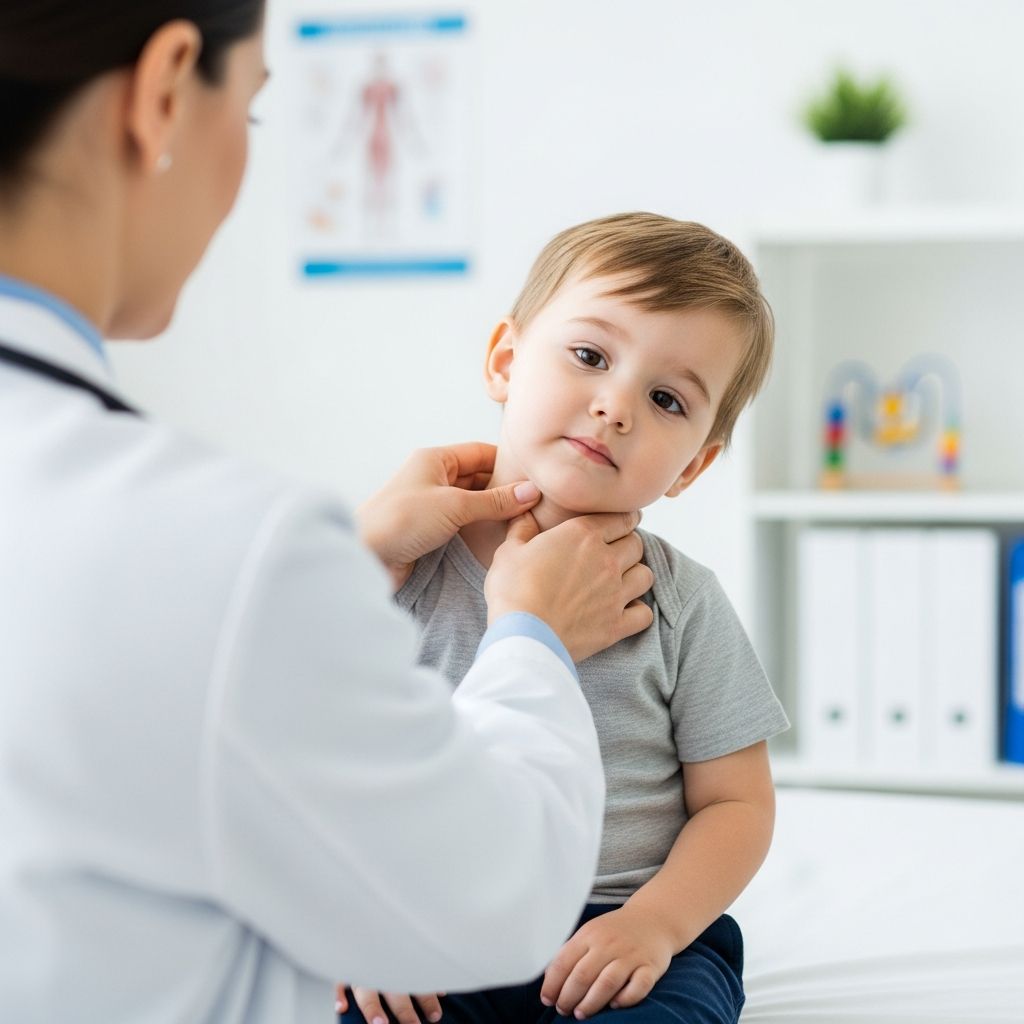
Neck muscle tightness causing a child’s head to tilt or turn is known as torticollis, a condition affecting infants and older kids alike. Early detection and targeted interventions often lead to full resolution.
Understanding Neck Tilt Conditions in Youngsters
Torticollis, sometimes called wryneck, involves involuntary contraction or shortening of neck muscles, primarily the sternocleidomastoid (SCM), leading to an abnormal head position. In babies, it often manifests as a persistent tilt where the head leans toward one shoulder while the chin points away. Older children might experience acute episodes with pain and limited mobility. This condition can be congenital, present at birth, or acquired later due to various triggers.
Distinguishing types is crucial: congenital muscular torticollis stems from SCM fibrosis or shortening, while acquired forms arise from inflammation, trauma, or neurological issues. Prevalence is notable, affecting about 1 in 250 infants for the congenital variant. Prompt recognition prevents secondary issues like facial asymmetry or motor delays.
Common Origins of Pediatric Neck Stiffness
Several factors contribute to torticollis in the young. For newborns, intrauterine positioning—such as limited space causing muscle strain—or breech delivery may damage the SCM, leading to fibrosis. Birth trauma, though rare, can stretch neck tissues excessively.
Acquired cases in infants and children often link to infections like retropharyngeal abscesses or upper respiratory illnesses, where lymph node swelling irritates neck muscles. Trauma, even minor like awkward sleeping postures, triggers spasms. Other culprits include gastroesophageal reflux (Sandifer syndrome), causing reflexive posturing, or ocular imbalances prompting compensatory tilts.
Rarer etiologies encompass neurological anomalies, posterior fossa tumors signaling with intermittent tilts plus vomiting, or atlantoaxial rotatory subluxation from pharyngeal inflammation (Grisel syndrome). Genetic factors or high muscle tone in conditions like juvenile idiopathic arthritis heighten risk.
Risk Factors Breakdown
- Infants: Breech position, firstborn status, oligohydramnios.
- Children: Recent infections, neck injuries, medication side effects.
- Both: Family history of dystonia, prematurity.
Recognizing Signs in Babies and Kids
Observe your child’s head posture closely. A hallmark is unilateral head tilt with contralateral chin rotation. Infants may resist turning toward the affected side during play or feeding, preferring one direction. Palpate for SCM swelling or a firm mass, common in congenital cases.
Pain varies: congenital often painless, while acquired brings tenderness on movement or pressure. Accompanying symptoms signal urgency—fever, drooling, swallowing difficulty, or neurological signs like headaches warrant immediate evaluation.
| Symptom | Congenital | Acquired |
|---|---|---|
| Head Tilt | Persistent, painless | Sudden, often painful |
| Neck Mass | Fibrous lump in SCM | Swelling from infection/trauma |
| Mobility | Limited rotation to one side | Stiffness, spasms |
| Associated Issues | Plagiocephaly, facial asymmetry | Fever, vomiting if serious |
Secondary effects include flat head spots (positional plagiocephaly), uneven shoulder heights, or delayed milestones like rolling.
Diagnostic Approaches for Young Patients
Pediatricians start with history and physical exam, assessing neck range and SCM integrity. Ultrasound confirms congenital fibrosis; X-rays rule out bony issues or subluxations. MRI probes neurological causes if symptoms persist. Dynamic imaging like CT may evaluate rotatory displacements.
Consult specialists—ENT for abscesses, ophthalmology for ocular torticollis, neurology for tumors. Early diagnosis, ideally before 3 months, optimizes outcomes.
Home-Based Management Strategies
Conservative care forms the backbone. Repositioning is key: alternate carrying positions, limit time in car seats or swings facing one way. Tummy time builds strength—aim for 15-30 minutes daily, increasing gradually.
Gentle stretches target the tight SCM. Perform 3-5 times daily:
- Chin-to-Shoulder Turn: Hold baby upright, gently rotate chin to non-preferred side, hold 10 seconds.
- Head Tilt Stretch: Support head, ease ear toward opposite shoulder.
- Neck Extension: Encourage looking up while stabilizing shoulders.
Apply warm compresses pre-stretch to relax muscles; follow with massage. Track progress with photos. Consistency yields improvements in weeks.
Professional Therapies and Interventions
Physical therapy (PT) is gold standard, with therapists teaching customized exercises, strengthening weak extensors, and using positioning aids. Helmets correct severe plagiocephaly if needed.
Botulinum toxin injections relax spastic muscles in refractory cases; surgery, rare, releases fibrotic SCM after 12-18 months. Address underlying issues: antibiotics for infections, reflux management for Sandifer.
Prognosis excels—90% resolve with PT by age 1 if treated early. Delays risk permanent asymmetry.
Preventive Measures for Healthy Neck Development
Promote varied positions from birth: alternate feeding sides, use mirrors to encourage turning. Limit container time; prioritize interactive play. Monitor during illnesses for new tilts.
Parental education via well-child visits catches issues early. Diverse positioning fosters symmetrical growth.
Potential Complications and Long-Term Outlook
Untreated torticollis risks facial scoliosis, jaw misalignment, vision deficits, or motor delays. Older kids face chronic pain or dystonia.
With intervention, most achieve normal alignment. Monitor milestones; follow up quarterly in therapy.
Frequently Asked Questions
Can torticollis resolve without treatment?
Some mild cases improve spontaneously, but most benefit from stretches and PT to prevent complications.
Is torticollis linked to vaccines or teething?
No direct link; infections around these times may trigger acquired forms.
How long do stretches take to work?
Visible changes in 4-6 weeks with daily practice; full resolution may take months.
When is surgery necessary for babies?
Rarely before age 1; only if non-responsive to conservative care.
Does torticollis affect sleep positions?
Yes—encourage back sleeping with head alternation using wedges or rolls.
References
- Torticollis | Nemours KidsHealth — Nemours Children’s Health. 2023. https://kidshealth.org/en/parents/torticollis-kids.html
- Torticollis in infants and children: common and unusual causes — PubMed (PubMed ID: 16958498). 2006-09-01. https://pubmed.ncbi.nlm.nih.gov/16958498/
- Torticollis (Wryneck): Symptoms, Causes & Treatment — Cleveland Clinic. 2023-07-27. https://my.clevelandclinic.org/health/diseases/22430-torticollis
- Torticollis – Seattle Children’s Hospital — Seattle Children’s. Accessed 2026. https://www.seattlechildrens.org/conditions/torticollis/
- Torticollis – treatments, symptoms, causes and prevention — healthdirect (Australian Government). Accessed 2026. https://www.healthdirect.gov.au/torticollis