

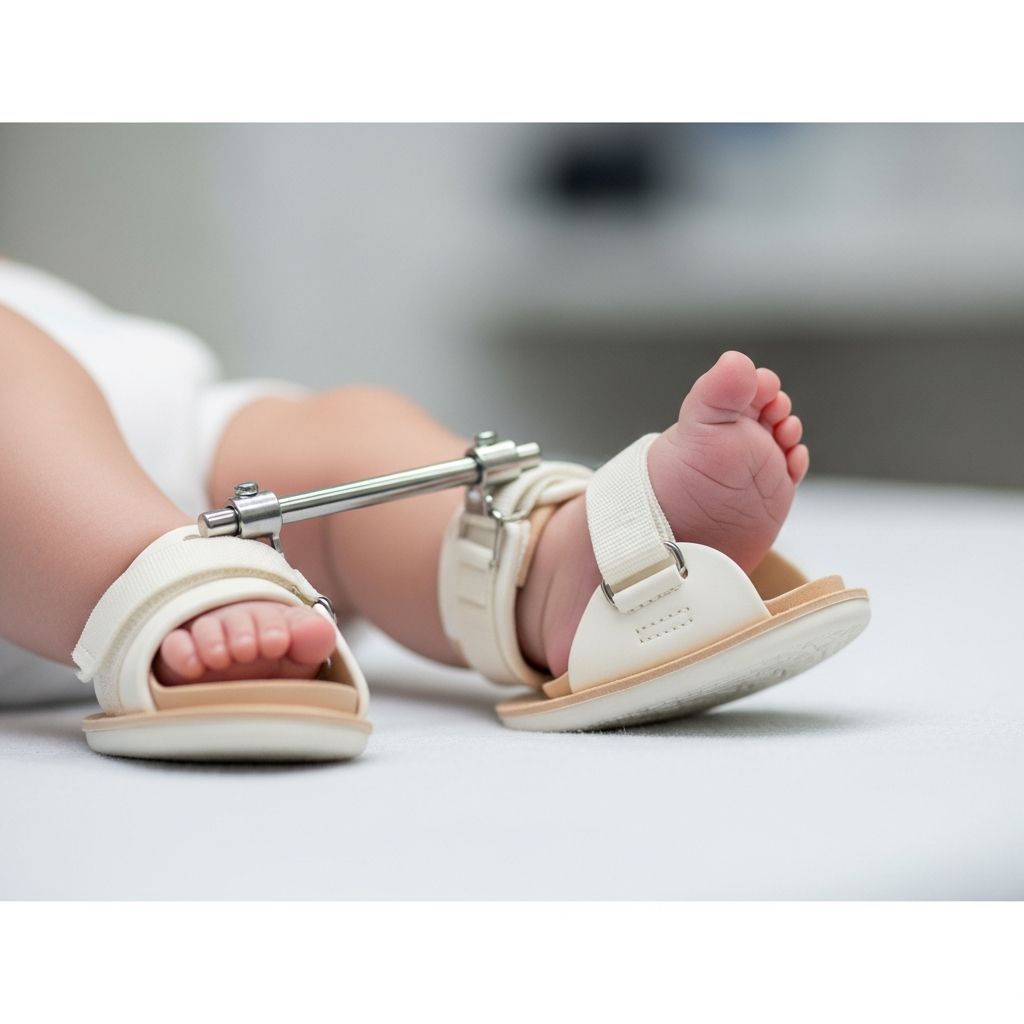
The Ponseti method represents a gold standard in treating congenital clubfoot, a condition where a baby’s foot turns inward and downward. After initial casting and a minor tendon procedure correct the foot’s alignment, the **bracing phase** becomes crucial to hold these gains and prevent the deformity from returning. This phase uses a specialized device called a foot abduction orthosis (FAO) to maintain the foot in an outward-rotated, corrected position.
Understanding Clubfoot and the Ponseti Approach
Clubfoot, or congenital talipes equinovarus (CTEV), affects about 1 in 1,000 newborns, twisting the foot into a pointed-down, turned-in shape due to tight tendons and ligaments. Untreated, it can lead to pain, mobility issues, and the need for surgery. The Ponseti method avoids major operations through gentle, weekly manipulations and long-leg casts over 4-8 weeks, often followed by a quick Achilles tenotomy—a small cut to lengthen the tendon.
Success rates exceed 95% when fully followed, yielding functional, shoe-friendly feet. However, without bracing, relapse occurs in up to 50-80% of cases because infant tissues naturally revert. Bracing stretches these tissues over years, promoting permanent correction.
The Role of Bracing in Long-Term Success
Bracing starts right after the final cast removal, typically at 8-12 weeks of age. It counters the foot’s tendency to relapse by holding it abducted (turned outward) at 60-70 degrees, with slight dorsiflexion (upward tilt). This position aligns the talus bone properly under the tibia, stabilizing the ankle and hindfoot.
Studies show strict brace adherence drops relapse to near zero, versus high rates with poor compliance. The brace works passively during sleep and rest, gradually remodeling ligaments without discomfort when fitted right.
Types of Ponseti Braces
Several brace designs exist, but all feature a rigid bar connecting open-heeled shoes or boots, keeping feet externally rotated and separated. Common options include:
- Standard Foot Abduction Orthosis (FAO): Aluminum or plastic bar (shoulder-width long) with adjustable shoes. Most common for home use.
- Ponseti Boots with Bar: Soft boots attached to a bar, allowing some knee flexion. Ideal for active toddlers.
- Hybrid Braces: Variations with straps for easier application, used in some clinics.
| Brace Type | Key Features | Best For |
|---|---|---|
| Standard FAO | Rigid bar, open-toe shoes, 70° abduction | Infants 3 months to 4 years |
| Ponseti Boots | Flexible boots, adjustable bar | Active children, nap use |
| Steenbeek Brace | Low-cost, locally made | Resource-limited settings |
Orthotists customize braces based on the child’s size, severity, and bilateral/unilateral clubfoot status. Regular check-ups ensure proper fit as the child grows.
Bracing Schedule: A Timeline for Compliance
The protocol is precise to maximize effectiveness:
- Weeks 1-12 post-casting: Full-time wear (23 hours/day), removing only for baths and stretches. Ensures initial stability.
- Weeks 13-16: 15-18 hours/day, allowing short diaper-free periods.
- Age 4 months to 3-4 years: Nighttime and naps only (8-10 hours/night). Continue until at least age 4, or 5 for severe cases.
Follow-up visits every 1-3 months monitor progress. Adjustments prevent skin issues or slippage.
How to Apply and Use the Ponseti Brace Properly
Correct application prevents sores and ensures efficacy. Steps include:
- Dress child in a onesie or loose clothing over the brace.
- Place feet into shoes/boots with heels fully seated.
- Secure straps snugly but not tightly—two fingers should fit under.
- Attach shoes to bar at prescribed angles: 70° external rotation for affected foot, 30-40° for unaffected.
- Knees slightly bent (10-20° flexion).
- Check for pressure points; adjust weekly.
Pro tip: Use a changing table for support. Videos from clinics demonstrate techniques. Daily skin checks are vital—redness should fade within 30 minutes of removal.
Common Challenges and Practical Solutions
Bracing demands parental commitment, but hurdles are manageable:
- Crying/Fussiness: Babies adapt in 1-2 weeks. Use white noise, swaddling, or feed during application.
- Skin Irritation: Apply lotion to clean, dry skin. If persistent, consult orthopedist for padding or refit.
- Sleep Disruption: Brace before drowsy; many sleep better once routine-set.
- Growth Spurts: Measure bar length monthly; replace every 3-6 months.
- Travel/Compliance: Pack extras; apps track wear time.
Support groups via Ponseti associations offer tips from experienced parents.
Monitoring Progress and Preventing Relapse
Signs of issues include foot turning in, limping, or pain. Monthly ortho visits assess range of motion—full correction allows 15° dorsiflexion, 70° abduction. If relapse occurs (10-30% with non-compliance), recasting and tenotomy repeat, followed by stricter bracing.
By age 5, most graduate to normal shoes/activities. Long-term, Ponseti kids run, play sports, with minimal arthritis risk.
Benefits Beyond Correction
Ponseti bracing yields plantigrade, mobile feet for normal gait. Kids avoid surgeries (64% reduction vs. older methods), wear standard shoes, and achieve pain-free mobility into adulthood. Economically, it’s cost-effective, especially in low-resource areas with local braces.
Frequently Asked Questions (FAQs)
What if my child refuses the brace?
Consistency pays off—most adapt quickly. Distract with toys/songs; consult for custom fits if needed.
How often should we replace the brace?
Every 3 months for infants, 6 months for toddlers, or at growth signs like heel lift.
Can bracing affect walking?
No—timely bracing promotes normal development. Delays stem from untreated clubfoot.
Is tenotomy always needed before bracing?
In 60-90% of cases for full correction; it’s safe, outpatient, and tendon regrows longer.
What if we miss brace nights?
Even partial compliance helps, but full adherence minimizes relapse risk to <2%.
Partnering with Healthcare Providers
Success hinges on trained teams—orthopedists, orthotists, physical therapists. Global programs train providers via Ponseti International. Parents: Attend all appointments, voice concerns early.
In summary, Ponseti bracing transforms clubfoot management, offering a non-surgical path to healthy feet. With diligence, families see their children thrive unrestricted.
References
- Ponseti method – Physiopedia — Physiopedia. 2023. https://www.physio-pedia.com/Ponseti_method
- Treatment of Clubfoot Using the Ponseti Method — PubMed (StatPearls). 2018-09-09. https://pubmed.ncbi.nlm.nih.gov/30233921/
- The Ponseti Method for Clubfoot Correction — Hospital for Special Surgery (HSS). 2023. https://www.hss.edu/health-library/conditions-and-treatments/the-ponseti-method-for-clubfoot-correction
- The Ponseti Method: Bracing Phase — Nemours KidsHealth. 2023. https://kidshealth.org/en/parents/ponseti-bracing.html
- Ponseti Method for Clubfoot in Children — NYU Langone Health. 2023. https://nyulangone.org/conditions/clubfoot-in-children/treatments/ponseti-method-for-clubfoot-in-children
- Bracing Tips — Ponseti International Association, University of Iowa. 2023. https://ponseti.medicine.uiowa.edu/parent-information/bracing-tips



