Appendicitis affects thousands of children each year, often requiring swift medical intervention to prevent serious complications. This guide explores the condition’s causes, diagnostic approaches, primary treatment methods like surgery and antibiotics, recovery expectations, and strategies for supporting your child through the process. Understanding these elements empowers parents to make informed decisions alongside healthcare providers.
Understanding Appendicitis: What Parents Need to Know
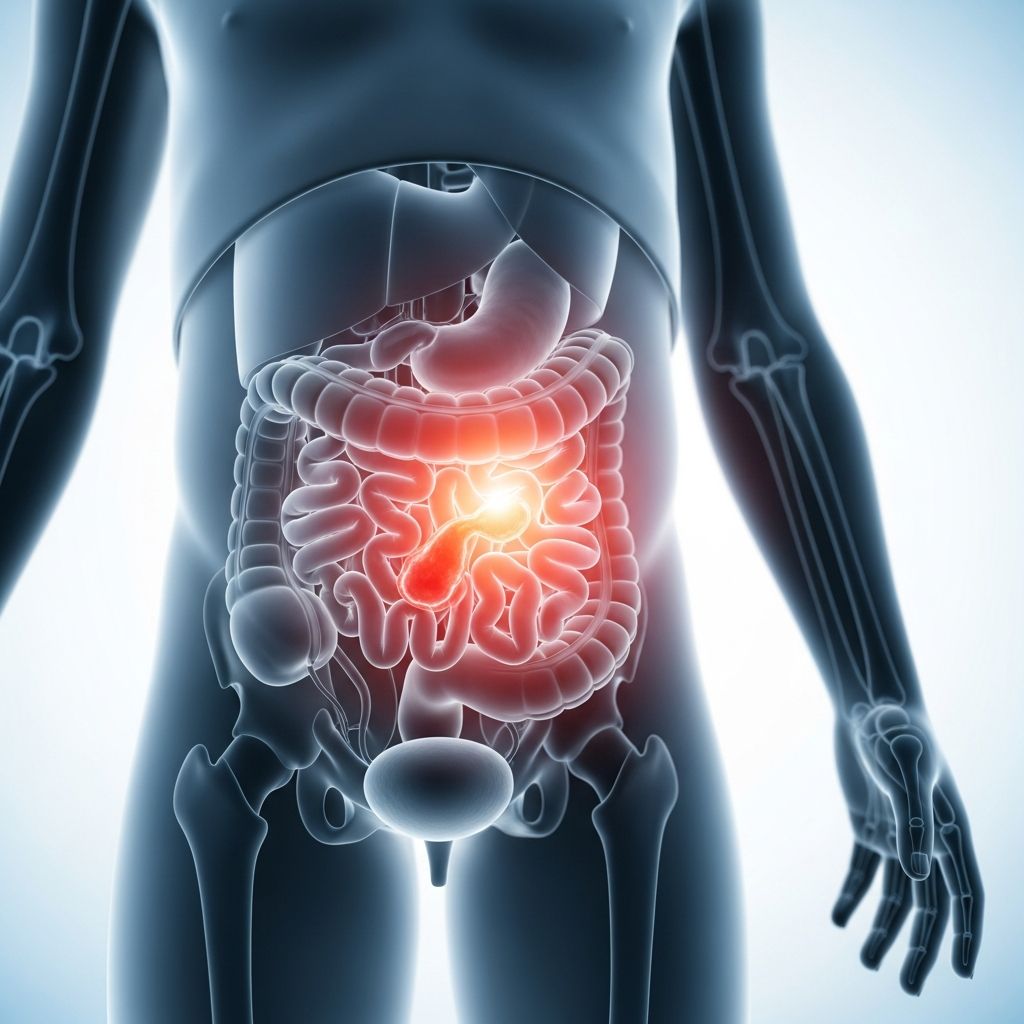
The appendix is a small, tube-like organ attached to the large intestine. When it becomes inflamed, typically due to blockage by stool, infection, or foreign material, appendicitis develops. In children, this condition can progress rapidly, leading to pain, fever, and digestive issues. Early recognition is crucial because a ruptured appendix can cause peritonitis, a life-threatening infection of the abdominal cavity.
Children may experience abdominal pain starting near the belly button and shifting to the lower right side, accompanied by nausea, vomiting, loss of appetite, and low-grade fever. Unlike adults, kids might not articulate symptoms clearly, making parental vigilance essential. Prompt evaluation by a pediatrician or emergency department can confirm the diagnosis through physical exams, blood tests, and imaging like ultrasound or CT scans.
Diagnostic Process for Pediatric Appendicitis
Diagnosing appendicitis in children involves a multi-step approach. Doctors begin with a history and physical exam, checking for tenderness in the right lower abdomen using techniques like the McBurney’s point test. Blood work reveals elevated white blood cell counts indicating infection, while urinalysis rules out urinary tract issues.
Imaging plays a pivotal role. Ultrasound is preferred in children to minimize radiation exposure, visualizing an enlarged appendix or fluid collections. If inconclusive, a CT scan provides detailed images but is used judiciously. In select cases, diagnostic laparoscopy allows direct visualization. Accurate diagnosis prevents unnecessary surgeries while ensuring timely treatment.
Surgical Intervention: The Gold Standard Treatment
Appendectomy, the surgical removal of the appendix, remains the cornerstone of treatment for most cases of pediatric appendicitis. Performed under general anesthesia, it can be done via open surgery or laparoscopy. Laparoscopic appendectomy uses small incisions and a camera, offering faster recovery, less pain, and reduced infection risk.
Timing is critical: surgery within 24-48 hours of symptom onset yields the best outcomes. For uncomplicated cases without perforation, patients often go home within a day. Antibiotics are administered pre- and post-operatively to combat infection. According to Cleveland Clinic guidelines, this combined approach ensures high success rates with minimal complications.
Non-Surgical Options: Antibiotics as an Alternative
Recent research has explored antibiotics as a primary treatment for uncomplicated appendicitis, particularly without appendicolith (a fecal stone blocking the appendix). A meta-analysis of pediatric studies found antibiotics effective in 90.5% of cases initially, with intravenous broad-spectrum drugs like piperacillin-tazobactam followed by oral amoxicillin-clavulanate.
However, failure rates are higher—up to 36% within a year—especially with appendicolith present, where 50% may require eventual surgery. Mayo Clinic notes antibiotics before surgery for perforated cases, but for non-perforated uncomplicated appendicitis, surgery is preferred due to lower recurrence risk. Parental discussion with surgeons weighs these options based on the child’s specific presentation.
| Treatment Type | Success Rate (Initial) | Recurrence Risk | Hospital Stay |
|---|---|---|---|
| Laparoscopic Appendectomy | 95-99% | None | 1-2 days |
| Antibiotics Alone | 90-92% | 20-36% at 1 year | 2-5 days |
This table summarizes key comparisons from recent meta-analyses, highlighting surgery’s definitive nature versus antibiotics’ potential for recurrence.
Handling Complicated Cases: Perforation and Abscess
When appendicitis perforates, forming an abscess, immediate surgery may not be ideal. Instead, initial management involves IV antibiotics via a PICC line for 10-14 days and percutaneous drainage under imaging guidance. St. Louis Children’s Hospital describes this as interval appendectomy, performed 6-8 weeks later once inflammation subsides.
Children with perforation face longer hospital stays, higher complication risks like wound infections, and potential need for bowel rest via NG tube. Close monitoring prevents sepsis. Recovery from complicated appendicitis takes weeks, emphasizing the importance of early intervention.
Preparing Your Child for Appendectomy
Pre-surgery preparation reduces anxiety. Explain the process simply: “The doctor will remove a small part that’s not working well using tiny tools through small cuts.” Fasting is required, typically from midnight. Hospitals provide child life specialists for distraction techniques like games or virtual reality.
Anesthesia teams ensure safety, monitoring vitals closely. Post-op, pain management uses acetaminophen or ibuprofen, avoiding opioids when possible. Encourage light activity to prevent clots.
Recovery Timeline and Home Care Tips
Most children resume normal activities within 1-2 weeks post-laparoscopy. Diet starts with clear liquids, advancing to solids. Watch for signs of complications: fever over 101°F, worsening pain, redness at incisions, or vomiting.
- Day 1-2: Rest, hydration, pain meds as prescribed.
- Week 1: No strenuous activity; sponge baths only.
- Week 2: Return to school if fever-free; resume sports after 4 weeks.
Nutritional support with high-fiber foods prevents constipation. Emotional care addresses fears through open talks.
Potential Risks and Complications
While rare, risks include bleeding, infection (5-10%), or bowel injury. Perforated cases elevate abscess or adhesions risk. Long-term, post-appendectomy syndrome mimics IBS but is uncommon. Regular follow-ups track growth and scarring.
A Cleveland Clinic review affirms low mortality (<1%) with modern techniques. Antibiotics carry side effects like diarrhea from C. difficile.
When to Seek Emergency Help
Act immediately if your child has severe abdominal pain, high fever, rapid heartbeat, or distended belly. Do not give laxatives or enemas, as they risk rupture. ER visits ensure rapid imaging and intervention.
Long-Term Outlook After Treatment
Life without an appendix is normal; the organ has no essential function. Some studies suggest minor microbiome changes, but no increased infection risk. Routine check-ups suffice. Recurrent appendicitis is impossible post-appendectomy.
Frequently Asked Questions (FAQs)
Can appendicitis resolve without surgery?
Antibiotics may resolve uncomplicated cases in 90% initially, but 20-36% recur within a year, per meta-analyses. Surgery eliminates recurrence.
How long does laparoscopic surgery take?
Typically 30-60 minutes, with 1-2 days hospital stay for children.
What diet is best post-surgery?
Start with clear liquids, progress to bland foods; high-fiber after a week to ease bowel movements.
Is appendicolith a concern for antibiotics?
Yes, 50% failure rate; surgery recommended if present.
Can my child return to school right away?
Usually after 1 week if uncomplicated, avoiding contact sports for 4 weeks.
Empowering Parents: Prevention and Awareness
While not fully preventable, hygiene reduces infection risk. Educate on symptoms via pediatric resources. Shared decision-making with providers balances risks and benefits.
This comprehensive approach ensures children receive optimal care, minimizing long-term impacts.
References
- Comparison of Antibiotic Therapy and Appendectomy for Acute Uncomplicated Appendicitis in Pediatric Patients: A Meta-analysis. — JAMA Surgery (PMC). 2017-06-07. https://pmc.ncbi.nlm.nih.gov/articles/PMC5470362/
- Appendicitis management: Is it time for a change? — Cleveland Clinic Journal of Medicine. 2022-06-01. https://www.ccjm.org/content/89/6/309
- Appendicitis in Children: Causes, Symptoms, Diagnosis and Treatment. — St. Louis Children’s Hospital. 2023-01-15. https://www.stlouischildrens.org/conditions-treatments/appendicitis
- Appendicitis – Diagnosis and treatment. — Mayo Clinic. 2024-05-10. https://www.mayoclinic.org/diseases-conditions/appendicitis/diagnosis-treatment/drc-20369549
- Appendicitis: Signs, Symptoms and Treatment. — Cleveland Clinic. 2023-11-20. https://my.clevelandclinic.org/health/diseases/8095-appendicitis