Fallopian tubes serve as vital pathways connecting the ovaries to the uterus, facilitating egg transport and fertilization. When these tubes become obstructed, it disrupts natural conception, leading to a condition known as tubal factor infertility that impacts up to 30-40% of infertility cases worldwide. This comprehensive guide explores the underlying mechanisms, warning signs, evaluation techniques, and restoration options to empower individuals on their path to parenthood.
Understanding the Anatomy and Role of Fallopian Tubes
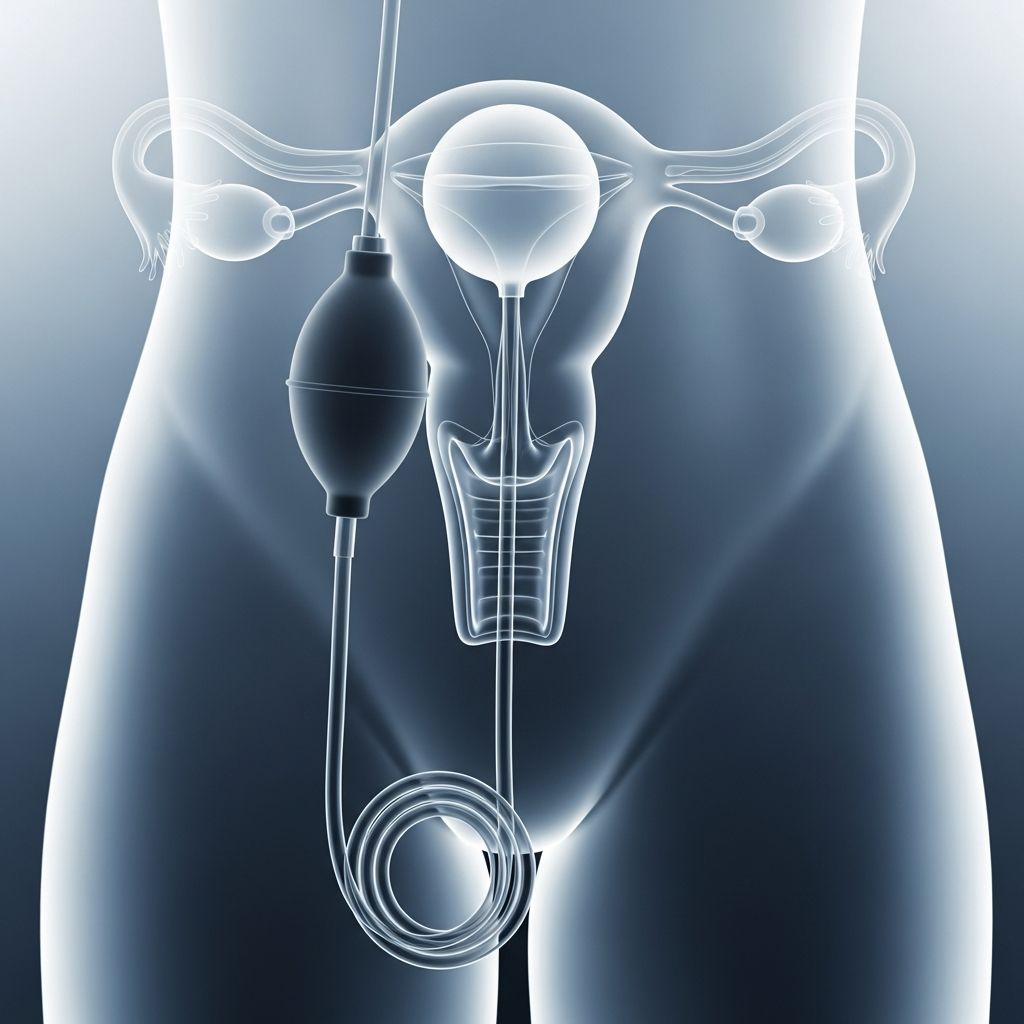
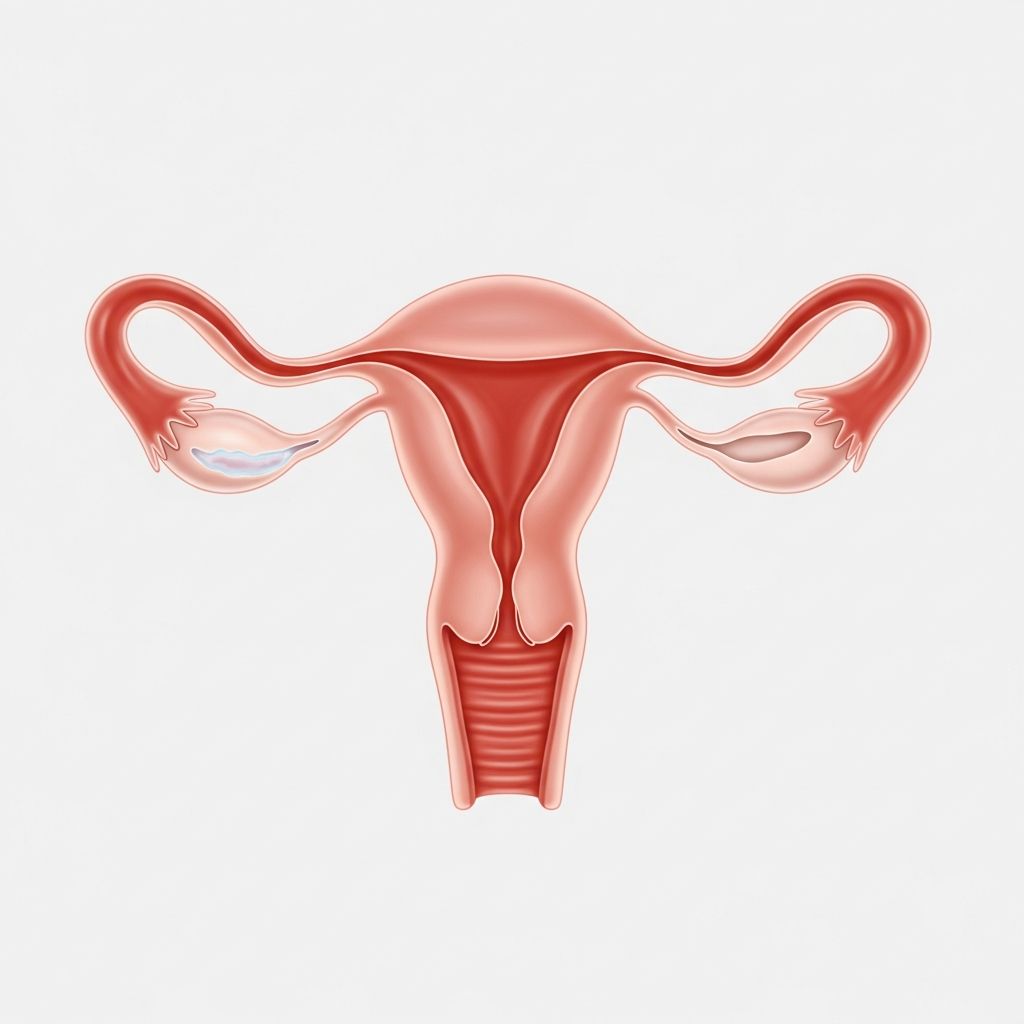
The fallopian tubes, also called oviducts, are paired muscular structures about 10-12 cm long, extending from each ovary to the uterus. Each tube features an outer fimbriated end that captures released eggs, a narrow central lumen lined with cilia for propulsion, and an inner connection to the uterine cavity. During ovulation, cilia and peristaltic waves guide the egg toward the uterus, where it meets sperm for potential fertilization. Blockages at any segment—proximal (near uterus), mid, or distal (near ovary)—prevent this process, often silently until fertility challenges arise.
Primary Indicators of Tubal Obstruction
Most cases of blocked fallopian tubes present asymptomatically, with infertility emerging as the primary clue after 6-12 months of unprotected intercourse. When symptoms occur, they stem from underlying conditions or complications like hydrosalpinx, where fluid accumulates distal to the blockage, distending the tube.
- Pelvic or abdominal discomfort: Dull, one-sided pain, especially during menstruation or intercourse, due to pressure from fluid buildup or inflammation.
- Abnormal vaginal discharge: Unusual odor or consistency from associated infections disrupting vaginal flora.
- Dysmenorrhea or dyspareunia: Intensified menstrual cramps or painful sex linked to endometriosis or pelvic inflammatory disease (PID).
- Urinary irritation: Rare discomfort during voiding if inflammation affects nearby structures.
- Recurrent pregnancy loss: Hydrosalpinx fluid may leak into the uterus, impairing embryo implantation.
These signs often overlap with other gynecological issues, underscoring the need for specialized fertility assessment.
Common Culprits Behind Tubal Blockages
Tubal obstructions result from scarring, adhesions, or structural anomalies, frequently tied to inflammatory or surgical histories. Understanding these origins is crucial for prevention and targeted intervention.
| Cause | Description | Risk Factors | Blockage Location |
|---|---|---|---|
| Pelvic Inflammatory Disease (PID) | Bacterial ascent from vagina/cervix causes salpingitis and scarring; chlamydia/gonorrhea primary pathogens. | Untreated STIs, multiple partners, IUD use. | Distal/hydrosalpinx. |
| Endometriosis | Ectopic endometrial tissue invades tubes or forms adhesions. | Family history, nulliparity. | Mid/proximal. |
| Prior Ectopic Pregnancy | Scarring from implantation/treatment in tube. | Tubal damage history, smoking. | Any segment. |
| Abdominal Surgeries | Adhesions post-appendectomy, C-section, or tubal ligation. | Multiple procedures. | Proximal/mid. |
| Fibroids or Polyps | Uterine growths distorting tube entry. | Age >35, obesity. | Proximal. |
PID remains the leading etiology, with studies indicating 10-15% of untreated chlamydia cases progress to tubal damage. Distal blockages often evolve into hydrosalpinx, where fimbriae fuse, trapping sterile fluid that swells the tube up to 5x normal size.
Diagnostic Approaches to Confirm Blockage
Early detection hinges on non-invasive imaging and office procedures, typically initiated during infertility workups.
- Hysterosalpingography (HSG): X-ray with contrast dye injected via cervix; reveals filling defects or spills at tube ends. Gold standard for proximal/distal patency; 80-90% accurate.
- Sonohysterography (SHG): Ultrasound-guided saline infusion to visualize tube outlines.
- Laparoscopy with Chromopertubation: Gold-standard surgery; dye instilled into tubes observed via camera for spills. Detects adhesions/endometriosis.
- Transvaginal Ultrasound: Identifies hydrosalpinx as dilated, fluid-filled tubes adjacent to ovaries.
- Chlamydia Antibody Test: Screens for past infection correlating with tubal risk.
HSG not only diagnoses but can occasionally dislodge mucus plugs, restoring patency in 20-30% of proximal cases.
Treatment Pathways: From Conservative to Advanced
Management prioritizes fertility preservation, balancing tube repair viability against age and blockage severity. Options span medical, surgical, and assisted reproductive technologies (ART).
Non-Surgical Interventions
- Antibiotics for active PID to halt progression.
- Tubal cannulation: Catheter threaded via hysteroscopy/fluoroscopy to clear proximal debris; success rates 20-40%.
Surgical Corrections
Laparoscopic adhesiolysis removes scar bands, while salpingostomy reopens distal ends. However, recurrence risks 20-40%, and peritubal damage often limits efficacy.
| Procedure | Purpose | Success Rate (Pregnancy) | Complications |
|---|---|---|---|
| Salpingectomy | Remove hydrosalpinx-affected tube. | 40-50% with IVF. | Ectopic risk reduction. |
| Salpingostomy | Open distal end, preserve tube. | 20-30% natural. | Fluid re-accumulation (20%). |
| Adhesiolysis | Lyse adhesions. | Variable, 15-25%. | Re-adhesion. |
For hydrosalpinx, salpingectomy prior to IVF doubles implantation rates by eliminating toxic fluid effects.
Assisted Reproduction
In vitro fertilization (IVF) bypasses tubes entirely: eggs retrieved, fertilized in lab, embryos transferred to uterus. Ideal for bilateral blockages or poor tube quality; live birth rates 40-60% per cycle under 35. Pre-IVF tube clipping or aspiration manages hydrosalpinx non-surgically.
Prevention Strategies for Reproductive Health
Proactive measures mitigate risks:
- STI screening/treatment: Annual chlamydia/gonorrhea tests for at-risk groups.
- Safe sex practices: Condom use reduces PID incidence by 50%.
- Timely endometriosis management: Hormonal therapy or excision surgery.
- Minimize surgical adhesions: Microsurgery techniques during necessary procedures.
Regular gynecologic care detects issues early, preserving tubal integrity.
Frequently Asked Questions About Blocked Fallopian Tubes
Can blocked fallopian tubes cause one-sided pain?
Yes, particularly with hydrosalpinx, where fluid buildup causes chronic unilateral abdominal discomfort.
Is HSG painful and safe?
Mild cramping occurs in 70%; ibuprofen pre-procedure helps. Complication rate <1%, including infection/allergy.
Can you get pregnant naturally with one blocked tube?
Yes, the patent tube compensates; 20-30% natural conception rate possible if other factors optimal.
Does hydrosalpinx affect IVF success?
It halves rates due to embryotoxic fluid; removal or drainage restores success to standard IVF levels.
How soon after diagnosis should treatment start?
Within 3-6 months if under 35; age impacts ovarian reserve, prioritizing IVF if tubes irreparable.
References
- Blocked Fallopian Tube – Symptoms, Causes, and Treatment — Ovoria. 2023. https://www.ovoria.com/blog/fertility/blocked-fallopian-tubes
- Blocked Fallopian Tubes — The Evewell. 2024. https://www.evewell.com/support/blocked-fallopian-tubes/
- Infertility Caused by Damaged or Blocked Fallopian Tubes — Loma Linda Fertility. 2023. https://lomalindafertility.com/infertility/women/blocked-fallopian-tubes/
- Blocked fallopian tubes: Symptoms, causes, and treatment — Medical News Today. 2023-10-01. https://www.medicalnewstoday.com/articles/321419
- Hydrosalpinx: Causes, Symptoms, Diagnosis & Treatment — Cleveland Clinic. 2024. https://my.clevelandclinic.org/health/diseases/24437-hydrosalpinx
- Fallopian Tube Blockage Treatment — San Diego Fertility Center. 2023. https://www.sdfertility.com/post/fallopian-tube-blockage-treatment
- Tubal Blockage: Causes, Symptoms, Treatments — Veritas Fertility. 2024. https://veritasfertility.com/conditions/tubal-blockage/